Chlorine does not kill Cryptosporidium, and it never gets to the Legionella growing in a building’s hot water. Six years of CDC surveillance shows the organisms that make the most people ill are not the ones that kill them.
24 September 2026·11 min read·By Kendal Rubow
In the spring of 1993, pharmacies across Milwaukee ran out of anti-diarrheal medicine. Absenteeism climbed at the city’s hospitals and schools. It took health officials days to work out what they were looking at, because the thing making people ill was arriving through a system that was, by every measure then in use, working.
Roughly 400,000 people fell ill. At least 69 died, most of them people living with AIDS. The cause was Cryptosporidium, a parasite that had passed through the filters at the city’s southern treatment plant. The water had been treated. It had been chlorinated. And none of that mattered, because chlorine does not kill Cryptosporidium.
Milwaukee remains the largest documented waterborne outbreak in United States history, and more than thirty years on it is still the clearest illustration of something most people find counterintuitive: the two organisms that matter most in drinking water are the two that ordinary disinfection does not reach.
The parasite that survives the chlorine
Part of what makes Cryptosporidium difficult is a matter of packaging. The parasite spends part of its life cycle sealed inside an oocyst — a thick-walled capsule between four and six micrometers across, spherical to oval, tough enough to survive conditions that would destroy a bacterium.
The Environmental Protection Agency’s health advisory on the organism is blunt about the consequence. Ozone is the most effective chemical disinfectant against it, with chlorine dioxide second. Conventional chlorination is not reliable. The Centers for Disease Control and Prevention puts it more plainly still: Cryptosporidium is “poorly inactivated by chlorine or iodine disinfection.”
It also does not take much. In human challenge studies cited by the EPA, 62 percent of subjects given thirty or more oocysts became infected. The dose that infected half of healthy adults worked out at roughly 132 oocysts — but that figure varied enormously between strains, from as few as 9 to as many as 1,042 depending on the isolate. A handful of organisms, in the wrong strain, is enough.
Because the chemistry does not work, the control has to be physical. Under the Interim Enhanced Surface Water Treatment Rule, filtered systems must achieve at least 2-log removal of Cryptosporidium — that is, 99 percent. It is worth sitting with the EPA’s own description of what good practice delivers: “a well-operated water filtration system is capable of removing at least 99 of 100 Cryptosporidium oocysts.”
That is an engineering tolerance, not a guarantee. Ninety-nine percent removal of a large number is still a number. Giardia, which also forms cysts and also tolerates chlorine far better than bacteria do, presents the same basic problem in a slightly more forgiving form.
What actually puts Americans in hospital
Here is where the intuition breaks down.
The CDC’s surveillance summary of drinking-water outbreaks covering 2015 through 2020 — the most recent full accounting — recorded 214 outbreaks across 28 states, causing 2,140 illnesses, 563 hospitalizations and 88 deaths.
Of those 214 outbreaks, 187 were biofilm-associated: organisms growing inside plumbing rather than arriving from the source. One hundred and eighty-four of them were Legionella. Only 24 outbreaks — 11 percent — were the enteric illnesses most people picture when they think of contaminated water: norovirus, Shigella, Giardia, Campylobacter, Cryptosporidium, E. coli.
Now look at who got hurt. Those 24 enteric outbreaks produced 1,299 cases — 61 percent of all illness in the period — but only 10 hospitalizations and no deaths at all. Legionella produced 786 cases, a little over a third of the total, and from that smaller number came 544 hospitalizations and 86 deaths: 97 percent of all hospitalizations and 98 percent of all deaths in six years of national surveillance.
The organisms that make the most people ill and the organisms that kill people are not the same organisms.
The hazard that grows after the treatment plant
Legionella is not a source-water failure. It is a building problem. The bacterium establishes itself in premise plumbing — the pipes, tanks, and fixtures downstream of the water main — where it shelters inside biofilm and multiplies in water that has sat warm for too long.
The contributing factors CDC recorded read like a maintenance audit rather than a treatment failure: Legionella already present in a building’s water system, temperature and disinfectant conditions that favor growth, water sitting at or above 86°F, and aging plumbing. By the time water has traveled through a large building, the disinfectant residual that protected it in the main has often decayed to nothing.
That is why the outbreaks cluster where they do. Hospitals, long-term care and assisted living accounted for 113 outbreaks — 53 percent of the total — and within them 372 hospitalizations and 75 deaths, which is 85 percent of all deaths recorded. Hotels and lodges accounted for another 35. These are buildings with long pipe runs, large hot water systems, low-flow guest rooms that sit unused, and populations who are already unwell.
There is one detail in that surveillance period worth noting for what it may signal. For the first time, Legionella was reported in three outbreaks traced to private residences, in 2015 and 2019.
Why you cannot drink your way into Legionnaires’ disease
This is the most widely misunderstood fact about the most lethal organism in American drinking water: you do not catch Legionnaires’ disease by drinking contaminated water. You catch it by breathing it — inhaling aerosolized droplets small enough to reach the lungs. Showers, cooling towers, decorative fountains, hot tubs and misters are the exposure routes that matter.
It follows that a boil-water notice, which is aimed squarely at organisms you swallow, does very little about Legionella. It is worth understanding what such a notice actually buys you. CDC guidance during a boil advisory is a rolling boil for one minute, extended to three minutes above 6,562 feet. Boiling does handle Cryptosporidium, which is precisely why it is the advice given when a treatment barrier has failed — heat succeeds where the chlorine could not.
Where boiling is impractical, CDC points to filters certified under NSF/ANSI Standard 53 or 58 for cyst removal or cyst reduction, to an absolute one-micron filter, or to reverse osmosis.
The indicator problem
Water utilities test constantly for coliform bacteria, and a clean coliform result is often reported as though it settles the question. It does not, and it was never meant to.
Coliforms are an indicator organism. Their presence suggests a pathway exists by which fecal contamination could be reaching the water; their absence suggests it probably is not. That is a genuinely useful signal, and it is not the same thing as a survey of what is in the water. A clean coliform test says nothing about Legionella multiplying in the hot water tank of the building you are standing in, and it is a poor proxy for chlorine-resistant parasites that behave nothing like the bacteria being counted.
Passing the test you are required to run is not the same as being free of the hazards you are not testing for. That is not an accusation against water utilities, which generally do difficult work well. It is a statement about what a test result means.
Where the regulation stops
Roughly 43 million Americans — about 15 percent of the population — drink from private wells. Those wells are not regulated by the federal government under the Safe Drinking Water Act, and, as the EPA notes, not by most state governments either. There is no mandatory testing, no required treatment, and no one who sends a report.
The outbreak data shows the shape of that gap. Individual and private systems accounted for just 17 outbreaks in the 2015–2020 period — 8 percent of the total — but 944 cases, which is 44 percent of all illness, and 14 deaths. Among enteric outbreaks where the water source could be identified, wells accounted for 13 of 14.
The causes were mostly structural rather than exotic. Contamination through limestone and fissured rock. Improper well construction. Flooding and heavy rain. And, in a quarter of enteric outbreaks, a treatment deficiency — most often no disinfection at all, sometimes no filtration.
The size of the problem
Outbreak surveillance captures clusters that someone noticed, investigated and reported. It is a floor, not a total. To estimate the real burden, CDC researchers modeled 17 pathogens across every water exposure route for a single year, 2014, and published the result in Emerging Infectious Diseases.
Their estimate: 7.15 million waterborne illnesses annually in the United States, around 601,000 emergency department visits, roughly 117,900 hospitalizations, about 6,630 deaths, and $3.33 billion in direct healthcare costs.
Drinking water specifically accounted for an estimated 1.13 million illnesses — but 47,700 hospitalizations, 3,300 deaths and $1.39 billion, the largest share of the cost. The pattern holds: drinking water produces fewer illnesses than recreational water and far more of the serious outcomes.
And the cost is dominated by organisms that grow in plumbing rather than organisms that arrive in it. Nontuberculous mycobacteria accounted for 46 percent of direct costs, followed by acute otitis externa at 17 percent, Pseudomonas pneumonia at 14 percent and Legionnaires’ disease at 12 percent.
What you can actually find out
If you are on a community water system, your utility is required to publish an annual Consumer Confidence Report. It will tell you what was detected, at what level, and against which limit. It is a genuinely informative document and almost nobody reads it.
What a CCR will not tell you is what happened to the water between the main and your tap, because that stretch is not the utility’s to monitor. The temperature of your water heater, how long water sits in unused lines, and the age and material of your plumbing are all on your side of the meter.
If you are on a well, the position is simpler and harder: nobody is testing it, so the only results that exist are the ones you pay for. State and county health departments generally maintain lists of certified laboratories.
The thirty years since Milwaukee have produced better filtration standards, tighter turbidity limits and a surveillance system that catches more than it used to. They have also revealed that the hazard moved. It is no longer mainly a question of what gets into the reservoir. It is increasingly a question of what grows in the pipes afterwards — and that is a part of the system no treatment plant can reach.
This article is general information about waterborne pathogens and public health data. It is not medical advice, and it does not describe or evaluate any particular treatment equipment. If you have a specific health concern, speak to your doctor; if you have a specific water concern, start with your utility’s report or a certified laboratory.
Every figure in this article comes from the published sources listed above. This is general information, not advice about the water at any particular address.
A Heritage is three stages, and each one is solving a different physics problem. One works by size, one works by chemistry, and one works by pressure across a membrane so fine that dissolved salts cannot follow the water through it.
Put together they handle a remarkably wide range of what can be in household water — microorganisms, sediment, chlorine and chloramine, industrial and agricultural chemicals, PFAS, microplastics, and at the kitchen tap the dissolved metals that nothing else catches. What follows is what each stage does, how the three hand off to each other, and the one maintenance decision you actually control.
Stage one: the ultrafiltration membrane
At the top of a Heritage is a four-inch by forty-inch stainless vessel holding an ultrafiltration membrane — a dense bundle of hollow fibers with a nominal pore size of 0.015 micron. It sits where the main enters the house, so everything downstream of it is already treated.
It works by size, and nothing else. Water passes through the fiber walls under household pressure. Anything bigger than the pore does not go with it. There is no chemistry, nothing is adsorbed, and no media is consumed — which is why this stage is cleanable rather than replaceable, and why it holds its performance instead of drifting toward a change-out date.
What the membrane takes out:
Microorganisms — bacteria including E. coli, protozoa, cysts, and most viruses.
Suspended solids and turbidity — fine dirt, silt, mud, cloudiness and suspended particles.
Macromolecules and organics — proteins, endotoxins, natural organic material and some high-molecular-weight organic compounds.
Debris — microplastics and algae.
The scale of it is easier to feel with a number attached. A Cryptosporidium oocyst measures roughly 4.8 to 5.6 micrometres and a Giardia cyst 8 to 19. Against a 0.015 micron pore, a Cryptosporidium oocyst is on the order of three hundred times too large to pass and a Giardia cyst closer to eight hundred times. Bacteria, at half a micron to two microns, are still thirty to a hundred and thirty times too big.
Everything to the right of the pore line is too large to pass. The dissolved minerals and metals to the left of it are what stages two and three are for.
The cyst performance is the part that carries independent certification: the membrane is certified to NSF/ANSI 53, tested against a challenge of more than 50,000 cysts per millilitre, and it achieved 99.99% average reduction. Cysts matter because the shell shrugs off chlorine at the doses a utility can legally use, which is why they sit behind a disproportionate share of documented waterborne outbreaks. Chemistry does not beat them. A pore smaller than they are does.
The membrane also protects everything behind it. Sediment, turbidity and colloidal material are intercepted here, so the carbon downstream never spends its capacity filtering dirt — it spends all of it on the chemistry it is actually good at.
One note for completeness, because it is on the manufacturer's own documentation: the system is not classified as a microbiological purifier. That is a specific EPA protocol for equipment intended to make unsafe water safe to drink, and it is a different thing from what this stage does on treated municipal supply. It is a stage that takes microorganisms out of water the utility has already disinfected — not a substitute for a boil notice.
Stage two: the carbon blocks
Behind the membrane sit two powdered carbon block cartridges, and this is the stage most people underestimate. A carbon block works two ways at once — chemical adsorption, where contaminant molecules bind to an enormous internal surface area, and mechanical filtration, because the powder is pressed into a solid block the water has to pass through rather than dosed loose the way a treatment plant does it.
What the carbon takes out:
Disinfectants and their byproducts — chlorine, chloramines, and trihalomethanes.
Organic chemicals and pollutants — volatile organic compounds, industrial solvents, fuels, pharmaceuticals and synthetic organic chemicals.
Pesticides and herbicides — agricultural runoff chemicals and weed killers, which matter more in this part of Oklahoma than most people assume.
Heavy metals — lead, mercury and copper, depending on the density and rating of the block.
Fine particulates and microplastics — sediment, rust, turbidity and microplastics down to sub-micron levels.
Biological cysts — Giardia and Cryptosporidium, in finer sub-micron block configurations.
Aesthetic impurities — bad tastes, musty odours and sulphur compounds.
On a Heritage specifically, the figure the manufacturer publishes is 99.95% chlorine reduction at every tap, shower and appliance in the house, and the cartridges carry NSF/ANSI 42 and CSA B483.1 certification for chlorine, taste and odour.
Chloramine, and why there are two cartridges
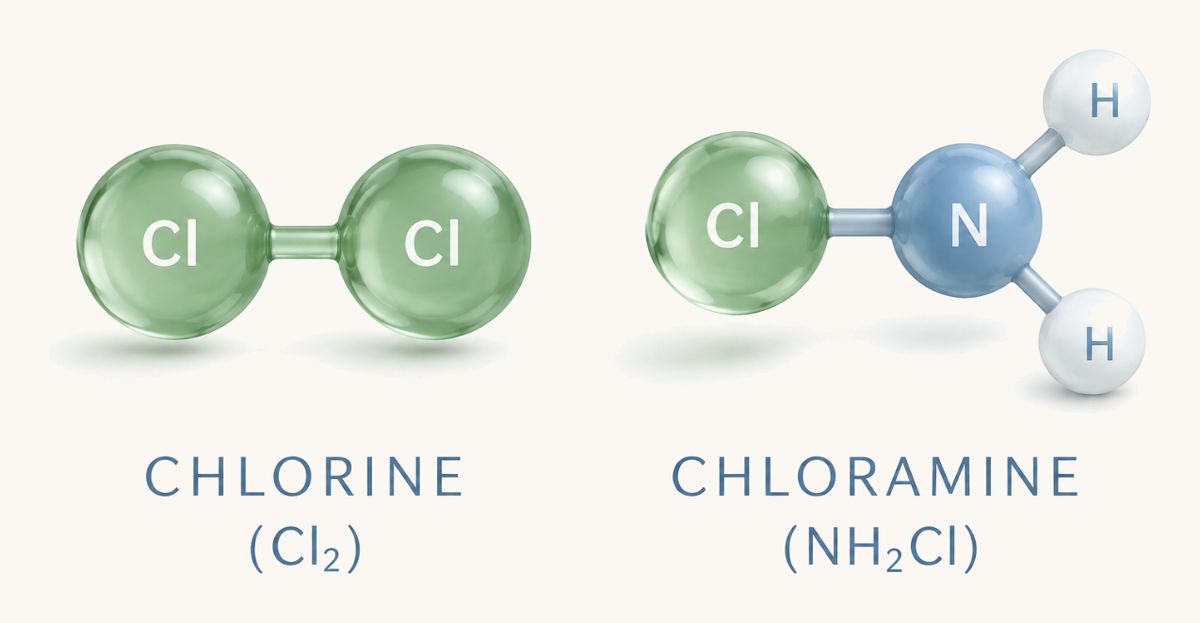
Worth knowing if you live here: Tulsa uses chloramine rather than free chlorine, and so do eleven of the fourteen metro systems. Carbon handles chloramine — the chemistry ends with nitrogen gas and chloride, the same harmless destination — but it is more stubborn than free chlorine and needs longer contact with more carbon to get there. The trade literature puts it at two to four times the contact time.
Which is exactly why a Heritage runs two cartridges in the post-filter manifold rather than one. At any given flow the water spends twice as long against carbon as a single-cartridge system allows. The configuration is a direct answer to the water this metro actually has. We wrote about chloramine at more length in a separate piece.
PFAS
Powdered carbon is one of the genuinely effective tools against PFAS, and the mechanism is worth understanding rather than taking on faith. PFAS molecules adsorb onto the vast internal surface area and microscopic pore structure of the carbon. The very fine particle size means they bind quickly, through a combination of Van der Waals forces, hydrophobic interaction and electrostatic attraction. Because the powder is formed into a solid block the water must travel through, every drop is forced into contact with that surface rather than flowing past it.
Scale control
The cartridges also carry food-grade polyphosphate, which holds calcium and magnesium in solution so the crystals cannot nucleate and bond to the inside of a pipe, a heating element or a fixture. It is the difference between a water heater element that stays clean and one that crusts over.
It is worth being precise about what this is, because the industry is often not. Sequestration is not softening. The minerals leave your tap still dissolved in the water, and a hardness test will read the same before and after — what changes is that the scale does not form. If what you want is the hardness number itself to come down, ion exchange is the technology that does it, with the salt, drain and regeneration cycle that comes with it. We laid out both options here.
Stage three: the Wellspring, at the kitchen tap
Lead, arsenic and fluoride are dissolved in water. They are not particles, so no filter with a pore size can catch them, and they do not adhere reliably enough to be a whole-home carbon claim. They need a different mechanism entirely — and this is the stage that supplies it.
Reverse osmosis pushes water through a membrane fine enough that the water molecules pass and the dissolved contaminants are left behind and flushed away. Certified to NSF/ANSI 58, held by the manufacturer, Nimbus Water Systems, for reduction of:
Lead
Arsenic (pentavalent)
Fluoride
Total dissolved solids
Cysts
A Wellspring is included with every Heritage, at no extra cost. It treats one tap — the water you drink and cook with, which is the water those contaminants actually matter in. And because it sits behind the whole-home stages, arriving water that has already had its chlorine, sediment and organics removed, its cartridge lasts about twice as long as the same unit would on its own.
Some water goes to the drain. That is not waste in the sense people assume — it is the mechanism. The reject stream is how the membrane carries the concentrated contaminants away instead of accumulating them.
How the three stages hand off
The design logic is simple once you see it laid out. Stage one removes what has size — organisms, sediment, organics, microplastics. Stage two removes what has chemistry — disinfectants, solvents, pesticides, PFAS, tastes and odours, and it controls scale on the way through. Stage three removes what is dissolved — the metals and ions nothing upstream can catch — at the one tap where that matters most.
Each stage also makes the next one work better. The membrane keeps dirt off the carbon so the carbon spends its life on chemistry. The carbon keeps chlorine off the RO membrane, which chlorine would otherwise damage, and doubles the life of its cartridge. Nothing in the chain is doing a job it is poorly suited to, which is the whole reason it is three stages instead of one very optimistic one.
The flush, and when to change it
Here is the part owners actually operate, and the part almost nobody is told about.
The ultrafiltration membrane is cleanable rather than consumable. What keeps it that way is the self-clean flush: a motorised valve reverses water across the fibers and carries the caught material out to drain. From the factory it runs once an hour for fifteen seconds, the duration is programmable between five and sixty seconds, and the schedule is set at the controller. You can trigger one by hand at the panel any time.
That flush is why the published membrane life reads "up to five years, source-water dependent" rather than a fixed replacement date. The phrase source-water dependent is an invitation to pay attention.
The gauges are the instrument, not the calendar
A Heritage has pressure gauges at the ultrafiltration outlet and at the post-filter stage. The number that matters is the difference between them, tracked over time at a consistent flow. A gradual rise in that difference is the long-established first indicator that a membrane is holding onto more than its flush is carrying away, and it shows up well before anything is noticeable at a tap.
So the most valuable five minutes of the whole ownership of this system happen in the first week. Open one bathtub tap wide, let it settle, and write both gauge readings and the date on a piece of tape stuck to the wall beside the unit. That is your baseline. Every later judgement is a comparison against it.
What changes the load
Heavy rain. Tulsa draws from Oologah, Spavinaw, Eucha and Hudson; Broken Arrow treats Verdigris River water. Storm runoff moves sediment into source water, and a wet stretch is the clearest case for shortening the interval for a few weeks.
Late summer. Warm water grows algae, and algal organic matter compacts into a membrane surface rather than rinsing off easily. If you shorten the interval once a year by default, this is when.
Winter, and a trap worth knowing. Cold water is around half again as viscous as summer tap water, so the same membrane passes less at the same pressure. That can look exactly like fouling on a gauge. It is physics, and it reverses in spring. Compare winter to last winter, not to last July.
Main breaks and street work. A city main repair pushes a slug of disturbed sediment down the line all at once. One manual flush after the notice goes out beats a month of schedule changes.
Shorten the interval when the pressure differential is climbing faster than it used to. Lengthen it when a full season passes with the differential flat. The hourly default is a sensible average, and plenty of homes never need to touch it. But your water comes from a specific plant, through specific pipes, in a specific season. The controller is adjustable because the water is variable, and the gauge on the wall is how the system tells you which way to move it.
Eventually a membrane does reach the end of its service life, and that is anticipated rather than surprising — it is what the five-year figure describes. When it arrives it is a part change, not a system replacement: the stainless vessel, the controller, the motorised valve, the manifold and the cartridge housings all stay exactly where they are. A cartridge system reaches a replacement date on a calendar whether your water earned it or not. This one tells you when.
The short version
Stage one, the UF membrane: bacteria, protozoa, cysts, most viruses, suspended solids and turbidity, proteins and endotoxins, natural organic material, microplastics and algae. Cyst reduction independently certified to NSF/ANSI 53 at 99.99% average.
Stage two, the carbon blocks: chlorine at 99.95%, chloramine, trihalomethanes, VOCs, solvents, fuels, pharmaceuticals, pesticides and herbicides, heavy metals, PFAS, microplastics, tastes and odours — plus polyphosphate scale control. Certified to NSF/ANSI 42 and CSA B483.1 for chlorine, taste and odour.
Stage three, the Wellspring RO: lead, arsenic, fluoride, total dissolved solids and cysts, at the kitchen tap. Certified to NSF/ANSI 58. Included with every Heritage.
That is a wide range of water chemistry for one wall of a utility room, and the reason it works is that no single stage is being asked to do a job it is wrong for. If you want to know which of it your own water actually calls for, the honest way to find out is to measure it — which is what the walkthrough is for, and it costs nothing.
There is a good chance the glass of water on your kitchen counter owes something to a courtroom in New Jersey. Not a laboratory. A courtroom.
In 1908, the private company supplying Jersey City began adding a small, carefully measured dose of chlorine to water drawn from the Boonton Reservoir. No American city had done that as a routine, continuous practice before. Within two years the method had been put on trial, and the verdict helped change how nearly every town in the country treats its water.
I went back through the record. The real story is better than the half-remembered version from a high-school science class.
The problem they were actually solving
Around 1900, typhoid was an ordinary part of American life. The CDC puts the rate at roughly 100 cases for every 100,000 people. It is a disease that travels largely through water contaminated with sewage, and cities were growing faster than anyone’s plan for keeping the two apart.
Sand filtration was already spreading and it helped. But a filter is a physical screen. Engineers of the day were learning that filtered water could still carry enough bacteria to make people sick. Something had to finish the job.
Two men and a very small dose
The idea came from John L. Leal, a physician who advised the Jersey City Water Supply Company. He had been experimenting with chlorine compounds and concluded that only a fraction of a part per million was needed to kill the bacteria that cause disease. That is the detail I find most striking: the breakthrough was not a big chemical hammer. It was precision.
The plant itself was designed by George Warren Fuller, a sanitary engineer with the New York firm Hering & Fuller. It fed a dilute solution of chloride of lime, known today as calcium hypochlorite, at roughly 0.2 to 0.35 parts per million. By one account that worked out to about five pounds of bleaching powder for every million gallons of water. Five pounds into a million gallons is a vanishingly small amount, which was exactly the point.
Why it ended up in court
Jersey City and its water company were already locked in a dispute over whether the supply met the terms of their contract, and the new chlorine plant landed squarely in the middle of it. Was adding a chemical an acceptable way to deliver clean water? Somebody had to decide.
That somebody was William J. Magie, a veteran New Jersey jurist, who heard the case as a special master. The trial ran more than thirty-eight days. It produced testimony from dozens of witnesses, hundreds of exhibits and more than 3,000 pages of record. Leal and Fuller both testified in support of the system.
On 9 May 1910, Magie ruled that the chlorine device could make the water “pure and wholesome.” In plain terms, a court looked hard at the evidence and concluded the method worked. The sanitary engineer C.-E. A. Winslow predicted the case would become one of the landmark lawsuits in the history of water supply, and he was right.
What happened next
The ruling opened the door, and cities walked through it quickly. According to Michael J. McGuire, an engineer who wrote a book-length history of the episode, more than 21 million Americans were drinking chlorinated water by 1914 — about 53 per cent of the roughly 40 million people then served by municipal systems, only six years after Jersey City flipped the switch.
The numbers that followed are some of the best news in American public health. The CDC reports that typhoid fell from about 100 cases per 100,000 people in 1900 to 33.8 by 1920. By 2006 it was down to 0.1, or 353 cases nationwide. The agency counts drinking water treatment among the ten great public health achievements of the twentieth century.
The honest footnote
An investigative piece should check its own favourite statistics, so here is one worth checking. A widely cited 2005 study by the economists David Cutler and Grant Miller credited clean water with a large share of the drop in American death rates in the early 1900s. Years later a team led by D. Mark Anderson, Daniel Rees and Kerwin Kofi Charles re-examined the data. They found transcription errors in about a fifth of the infant mortality figures and much weaker evidence for the broad claim.
What survived their review is still remarkable: filtering city water sharply reduced deaths from typhoid. The researchers on both sides shared data and worked it out in the open. That is how good science is supposed to go, and the core finding held.
What I take from this
The best water work is invisible. Nobody notices typhoid that never shows up, and that quiet is the success.
Getting it right was about measurement, not muscle. Leal’s insight was how little was needed.
The method earned its place with evidence. It went through a thirty-eight-day trial before most of the country adopted it.
Every time you fill a glass at the tap, you are drinking the result of an argument that was settled with data more than a century ago. That is worth a toast, preferably with water.
Yesterday I made a point about PFAS that I want to take back — carefully, and only partly.
I wrote that the carbon–fluorine bond is the strongest single bond in organic chemistry, that chemists built these compounds precisely because nothing breaks them, and that “forever chemicals” is not rhetoric but a description of a bond.
Every word of that is still accurate. But it describes the problem, not the state of the art. Because over the last few years a set of machines has arrived that does break it, and in April the EPA published a document that tells you exactly where the field stands.
That document is worth knowing about, because it is unusually honest.
The problem nobody talks about
Start with something uncomfortable about filtration, which is my own trade.
Activated carbon does not destroy PFAS. Reverse osmosis does not destroy PFAS. Ion exchange does not destroy PFAS. Every one of those technologies does the same fundamental thing: it takes PFAS out of the water and puts it somewhere else.
That somewhere else is a saturated carbon cartridge, a reverse osmosis concentrate stream, or a spent ion-exchange brine. The water leaving is cleaner. The PFAS has not gone anywhere — it has been gathered up and made portable.
For a household that is exactly what you want. The problem moves off your tap and into a cartridge you hand back. But multiply it by a country’s worth of treatment plants and you have collected an enormous quantity of a compound nobody could destroy.
Until recently there were three things you could do with it, and the EPA has now set them out formally.
What the EPA actually said in April
On 20 April 2026 the agency published its Interim Guidance on the Destruction and Disposal of PFAS, consolidating the research through September 2025. It covers three established, commercially available pathways.
Thermal treatment. Hazardous waste incineration, cement kilns, lightweight aggregate kilns. Combustion above 800°C with three to four seconds in the flame zone, and a regulatory requirement of 99.9999% destruction and removal efficiency. Air pollution control equipment is needed to capture the hydrogen fluoride that comes off.
Landfilling. Subtitle C hazardous waste cells with double composite liners, leachate collection and leak detection. The EPA is plain that this is containment, not destruction. The PFAS is still PFAS; it is behind engineering.
Underground injection. Class I wells, below 1,500 feet, isolated from drinking water. Practical mostly for liquids — reverse osmosis concentrate, ion-exchange brine — and only where the geology allows it, which in this country means the Great Plains rather than the coasts.
Burn it, bury it, or put it underground. Two of those three are storage.
The fourth category
Here is the part I find genuinely interesting, and it is where the EPA’s language rewards a close read:
“EPA partnered with industry and academia to collect data on emerging technologies for PFAS destruction, such as mechanochemical degradation, gasification and pyrolysis, and supercritical water oxidation. While the results from these studies show promise for PFAS destruction, further work using newly available methods is needed to more fully characterize the outputs of these processes.”
And then, more directly:
“In 2026, EPA is neither recommending nor discouraging the use of any emerging technology.”
Read that carelessly and it sounds like a shrug. Read it properly and it is a regulator saying: this works well enough that we are not going to stand in its way, and not yet well enough that we will put our name on it. Instead of a recommendation the agency published an evaluation framework — a way for a water utility or a base commander to judge these systems themselves.
That is the posture of a field that has moved from laboratory to field trial and is waiting on the paperwork.
What supercritical water actually is
The technology with the most real-world data behind it is supercritical water oxidation, and the physics of it is the best thing I have read all month.
Water has a critical point: 374°C and about 3,200 pounds per square inch. Push it past that and it stops being a liquid, and stops being steam, and becomes something else — a single dense phase that is neither.
In that state it behaves backwards. Ordinary water dissolves salt and refuses oil. Supercritical water dissolves oil and organic compounds freely, mixes with oxygen in any proportion, and drops salt out of solution as a solid.
So you have a fluid that will hold a PFAS molecule and an oxygen molecule in intimate contact, at a temperature where the carbon–fluorine bond finally has somewhere to go. The fluorine comes off as inorganic fluoride. The carbon leaves as carbon dioxide. The molecule is not moved. It is gone.
The field results, and why they surprised me
The best public demonstration ran at Peterson Space Force Base, treating firefighting foam waste — some of the most concentrated PFAS material that exists. The system ran at 625°C and 3,500 psi: hotter than a self-cleaning oven at full cycle, at roughly a hundred times the pressure in a car tyre.
Three runs, at three different concentrations:
Unconcentrated feed — 94.3% of PFAS destroyed.
50% concentrated — 99.2% destroyed.
79% concentrated — 99.7% destroyed, and this run met all five of the EPA’s maximum contaminant levels for regulated PFAS.
Look at the direction of that.
Every intuition says a treatment process should struggle as the contamination gets worse. This one improves. The dirtier the feed, the more completely it destroys what is in it.
There is a plain reason for it. The reaction is exothermic; PFAS destruction releases heat. A dilute feed is mostly water, and you spend your energy heating water that was not the problem. Concentrate it first and the reaction begins to sustain itself.
Which leads somewhere I did not expect when I started reading.
Filtration and destruction are the same job
If destruction works best on concentrated waste, then something has to do the concentrating.
That is precisely what a filter is for. Activated carbon takes PFAS out of thousands of gallons and holds it in a cartridge. Reverse osmosis splits a stream into clean water and a concentrate carrying everything that did not pass. Ion exchange loads a resin and releases it into a small volume of brine.
Every one of those is a concentration step. The destruction technologies are not a replacement for filtration — they are the second half of a process whose first half has existed for decades, and they get better at their end of the job the better filtration does at its own.
At Peterson the most concentrated run handled the smallest volume, 237 litres against 1,360 for the dilute run, and carried the most PFAS mass of any of them. That is the whole argument in one line: a small amount of very dirty water is a far easier thing to destroy than a large amount of slightly dirty water.
The filter makes the destruction possible. The destruction is what finally makes the filter’s output disposable.
What else is coming
Supercritical water oxidation is furthest along, but it is not alone, and the honest summary is that each of these is strong somewhere and awkward somewhere else.
Electrochemical oxidation. Passes current through the water and breaks the bond by direct electron transfer. In advanced pilots. The effective electrodes are boron-doped diamond, which works and is expensive, and the high potentials involved can generate chlorate and perchlorate that then need dealing with.
Non-thermal plasma. Better than 90% destruction of long-chain PFAS in a single pass, with field trials completed. Incomplete breakdown can leave shorter-chain PFAS behind, which is its main open question.
Thermal steam plasma. A core near 11,000 K, which dissociates essentially anything. Roughly 60% of the equipment footprint is gas scrubbing, and the fluorine comes out as a benign mineral product.
Hydrothermal alkaline treatment. 250 to 400°C under pressure, using hydroxide to attack the bond chemically rather than thermally. Needs a great deal of caustic, and the conditions are hard on equipment.
Sonolysis. Ultrasound, elegantly simple, completely mineralises what it treats, and consumes so much energy that it only makes sense on small concentrated streams.
Notice what nearly all of them have in common. They are best suited to concentrates. Again.
What this means at your kitchen sink
Nothing changes today, and that is not a disappointment.
None of this is household equipment. Supercritical water at 3,500 psi belongs on an industrial skid with a trained operator, not under anyone’s sink, and it will stay there.
What changes is the shape of the problem. For twenty years the honest answer about PFAS was that we could move it but not end it, and every filter in the country was writing cheques against a disposal system that did not exist. That is no longer the case. The disposal end is catching up, the EPA has published a framework for judging it, and the first field results are better than the people running them expected.
Meanwhile the household side of this was settled before the rule existed and has not moved. The EPA still names three technologies for reducing PFAS in home drinking water — granular activated carbon, ion exchange, and reverse osmosis — and certification under NSF/ANSI 53 or 58 for PFAS reduction is still the thing to look for, with those last three words still doing the work.
So the position is a good one. The thing you can control, you could already control. The thing you could not control — what happens to it afterwards — has spent five years quietly becoming solvable.
That is not a story about a chemical nobody can beat. It is a story about a bond that held out for seventy years and is now, in a few hundred litres at a time, starting to lose.
In September I wrote about Broken Arrow, where twenty-six people rang the city in eight days because the water smelled earthy. The compound responsible, MIB, is detectable by the human nose at about five parts per trillion. I made the point then that this is an extraordinary piece of biological equipment — instruments need a gas chromatograph to find what a person can find in a glass.
The federal limit for PFOA and PFOS in drinking water is four parts per trillion.
One part per trillion below where your nose gives out. That is the entire story of PFAS in a sentence: a category of compounds regulated at a concentration a human being has no way of perceiving, by any sense, ever.
This is not a frightening fact. It is a useful one, and it tells you exactly what kind of problem this is — a measurement problem, not a vigilance problem.
What they actually are
PFAS stands for per- and polyfluoroalkyl substances. There are thousands of them. What they share is a particular piece of chemistry: a chain of carbon atoms with fluorine attached.
The carbon–fluorine bond is the strongest single bond in organic chemistry. That is not a figure of speech; it is a measurable quantity, and it is why these compounds exist at all. Chemists built them precisely because nothing much breaks them. A molecule that shrugs off heat, water, oil and acid is exactly what you want in a non-stick pan, a waterproof jacket, a grease-resistant food wrapper, a firefighting foam that smothers a fuel fire.
The property that made them useful is the property that made them a problem. There is no elegant way around that, and there was no villain at the start of it — there was a genuinely brilliant piece of materials science whose consequences took decades to become visible.
"Forever chemicals" is a nickname doing real work. It is not rhetoric. It is a description of a bond.
Where the rule stands, which is a live question
This is the part most coverage gets muddled, so it is worth setting out plainly.
In April 2024 the EPA finalised the first national drinking water standards for PFAS. Six compounds were covered: PFOA and PFOS at 4.0 parts per trillion each, three others at higher thresholds, and a combined "hazard index" for mixtures.
In May 2026 the EPA moved on two fronts at once, and the two moves point in opposite directions.
It kept PFOA and PFOS. Administrator Zeldin's statement was direct: "We are on a path to uphold the agency's nationwide standards to protect Americans from PFOA and PFOS." The 4.0 parts per trillion figure stands.
It moved to rescind the other four — PFHxS, PFNA, GenX and the hazard-index mixture — to reconsider them through what the agency describes as the correct legal process.
And it proposed more time. Utilities currently have until 26 April 2029 to comply. The EPA has proposed extending that to 26 April 2031 for systems that request it. As of this writing that extension is a proposal, not a final rule.
Read that sequence honestly and it says something fairly reasonable: the agency is standing behind the two compounds with the deepest evidence base and giving water systems longer to do genuinely expensive engineering. Municipal PFAS treatment is not a filter change. It is new infrastructure, paid for out of rates.
What it also means, practically, is that the compliance date for your utility is somewhere between two and a half and four and a half years away, and a great deal of the country's monitoring data is still being gathered. EPA's fifth Unregulated Contaminant Monitoring Rule ran sampling from 2023 through 2025 for exactly this purpose.
What your own utility has to tell you
This is where it gets useful rather than abstract.
Every community water system in the United States publishes an annual Consumer Confidence Report. If your system tested for PFAS under the monitoring rule, those results are public. Tulsa, Broken Arrow, Owasso, Jenks, Bixby, Sand Springs — every one of them produces this document, and every one of them will send it to you.
Ask for it. Read the PFAS line. That single step replaces every assumption you might otherwise make in either direction.
And if you are on a private well, nobody is testing but you — the same situation I described with nitrate, for the same structural reason. Well water sits outside the federal drinking water framework entirely. That is not neglect; it is simply how the law is drawn.
Now the part I find genuinely encouraging
Here is what is unusual about PFAS compared with almost everything else I write about: the household treatment question is already settled, and it was settled before the rule existed.
The EPA names three technologies that reduce PFAS in home drinking water:
Granular activated carbon. The EPA's own description: "GAC materials are extremely porous, and the small pores trap the contaminants present in the water."
Ion exchange resin. Beads that act as "powerful ion magnets that attract and hold the contaminated materials."
Reverse osmosis. A membrane that separates dissolved material from water by forcing water through a barrier.
If you read my piece on nitrate, that first one should stop you.
Nitrate defeats activated carbon completely. It is small, stable and hydrophilic, it has no interest whatsoever in sticking to carbon, and it sails straight through. I called the carbon filter "not failing — it was never the right tool."
PFAS is the opposite case, and for a reason worth understanding.
A PFAS molecule has two ends. The fluorinated tail hates water. The head group likes it. That split personality — the technical word is amphiphilic, the same property that makes soap work — is what drives the molecule out of the water and onto any surface that will have it. Activated carbon offers an enormous amount of surface: a single gram has the internal area of a tennis court.
Two ends that want different things. The fluorinated tail is driven out of the water; the head group is perfectly content in it. Carbon gives the tail somewhere to go, and the molecule stays put. This is the same drawing as the reverse osmosis diagram in the nitrate piece, turned inside out — that one was about what fits through, this one is about what sticks.
So the same molecule that resists heat, acid and time is remarkably willing to leave the water and sit on a piece of carbon. The property that makes PFAS persistent in the environment is not the property that makes it hard to filter. Those are two different things, and conflating them is the single most common mistake in writing about this subject.
What to look for, specifically
The technology working is not the same as a given product working. That gap is closed by independent certification, and there are two standards that matter:
NSF/ANSI 53 — the standard for point-of-use filters, and the one that carries a PFAS reduction claim
NSF/ANSI 58 — the standard for reverse osmosis systems
The EPA's guidance is one sentence and I would not improve on it: "Look on product labels for certification under NSF/ANSI 53 or NSF/ANSI 58 for PFAS reduction."
Note the last three words. A filter certified under NSF/ANSI 53 for chlorine, or for cysts, has been tested for chlorine or for cysts. Certification is claim-specific. PFAS reduction is its own tested claim and it must be named. If a product page talks about NSF certification without saying what it was certified to reduce, that is the question to ask, and any honest supplier will answer it in a sentence.
Two practical notes, because you should know them going in. Carbon media has a finite capacity and must be changed on schedule — a saturated filter stops working long before it looks used. And reverse osmosis sends some water to the drain as part of the separation, though modern systems are markedly more efficient than older ones.
In return you get something worth having: a proven physical process, independently tested against this specific contaminant, working continuously at your tap while the regulatory calendar runs its course somewhere else.
What I take from this
Most of what I write about involves a gap — between what people can perceive and what the instruments say, between what a rule requires and what a customer expects.
PFAS has the widest gap of anything I have covered. Four parts per trillion is beneath sensation entirely. You will never taste it, never smell it, never see it, and no amount of paying closer attention will change that.
But the corresponding thing is also true, and it gets far less airtime: this is one of the few contaminants where you do not have to wait for anybody. The federal deadline is years out. The utilities are doing serious and expensive work in the meantime. And the household treatment has been established, certified and commercially available the entire time.
You cannot sense it. You can measure it — your utility already has. And you can treat it, today, with equipment that has been tested against this exact compound by somebody with no stake in selling it to you.
That is not a frightening story. It is an unusually well-lit one.
I want to start with the part that stopped me, because it is the part that stops most people.
Boiling your water does not remove nitrate. It concentrates it.
Not a little. The EPA puts it about as plainly as a federal agency ever puts anything: "Boiling water will NOT reduce nitrate levels. In fact, it will make the level of nitrate worse because some of the water will evaporate but the nitrate will not."
Think about what that means for a moment. Boiling is the oldest instinct we have about water. It is what our grandmothers did, what every emergency notice tells us to do, what I would have done without thinking. And for bacteria it is exactly right. For nitrate it is precisely backwards — you stand at the stove, the steam leaves, the nitrate stays, and what is in the pot at the end is stronger than what went in.
I find that genuinely fascinating rather than frightening, and I think it is worth understanding why.
What nitrate actually is
Nitrate is not an exotic industrial poison. It is nitrogen and oxygen, and it is one of the most ordinary substances on a working landscape.
It comes from fertiliser, because that is what fertiliser is for — nitrogen that plants can use. It comes from animal waste and septic systems. It comes from perfectly natural decay, from legumes fixing nitrogen in the soil, from plants doing what plants do. Rain moves it down through the ground, and groundwater carries it.
None of that is sinister. It is agriculture and biology going about their business. Oklahoma is farm country, and nitrogen is how farm country works.
What makes nitrate interesting is not where it comes from. It is how it behaves once it is in water.
You cannot find it with your senses
Most of what we notice in water announces itself. Chlorine has a smell. Iron leaves a stain. Hardness leaves a ring on the kettle and a film on the glass. Last week Broken Arrow could taste an algal bloom, and the calls started coming.
Nitrate does none of this. It is colourless, odourless and tasteless. Water with nitrate in it looks and tastes exactly like water without. There is no version of paying closer attention that will tell you it is there.
That is not a reason for alarm. It is simply a reason why this is one of the few things in water you have to measure rather than perceive.
Who it actually matters for
I want to be careful and honest here, because this is the part where water articles tend to reach for drama, and the facts do not need any.
The EPA's limit for nitrate in drinking water is 10 parts per million. Below that, public health agencies consider it safe.
The concern above that level is specific and well understood. Nitrate can interfere with how an infant's blood carries oxygen — a condition sometimes called blue baby syndrome. It is serious, it is rare, and it is concentrated almost entirely in babies under six months, particularly where formula is being mixed with well water. Pregnant women are also advised to pay attention.
For most healthy adults and older children, nitrate at the levels found in ordinary drinking water is not the thing to worry about.
So this is not a story about everyone being in danger. It is a story about a small number of households — new parents on a private well, mostly — for whom a simple measurement is genuinely worth taking. And it is a story about a problem with a clean, proven answer, which is the part I actually want to talk about.
The good news comes first
Nitrate is cheap to test for. It is one of the standard items on a basic water analysis, and Oklahoma State University Extension recommends that private well owners run an inorganic chemical panel every three to five years, and specifically that you test for nitrate if there is an infant under six months in the house.
If you are on city water — Tulsa, Broken Arrow, Owasso, Jenks, Bixby, Sand Springs — your utility is already testing for this, routinely, under federal rules, and is required to tell you if a standard is exceeded. OSU's own guidance notes that public supplies "present few concerns" for exactly this reason.
If you are on a well, nobody is testing but you. That is not a criticism of anyone; it is simply how private wells work. The water is yours, and so is the analysis.
Now the physics, which I love
Here is where nitrate stops being a worry and starts being interesting.
Most household water filters work by adsorption. Activated carbon is a sponge with an enormous internal surface area, and certain molecules stick to it as water passes through. Chlorine sticks. Many organic compounds stick. That taste-and-odour improvement people notice from a carbon pitcher is real and it is adsorption doing its job.
Nitrate does not stick. It is a small, stable, highly water-loving ion, perfectly content dissolved where it is, with no interest whatsoever in the carbon. Water goes in, water comes out, the nitrate rides along untouched. This is why the EPA is explicit that activated carbon filters — Brita pitchers among them — do not remove nitrates. The filter is not failing. It was never the right tool.
Reverse osmosis works on a completely different principle, and that is the whole point.
An RO membrane does not try to make anything stick. It is a barrier with openings so small that the question becomes simply: what fits?
Water molecules fit. They are tiny. Almost nothing else does — not dissolved salts, not metals, not nitrate. Push water against that membrane under household pressure and the water goes through while the dissolved passengers are left behind and flushed away.
It is size exclusion rather than chemistry. A doorway rather than a sponge. And because nitrate's defining trait is that it stays dissolved and refuses to stick to things, a method that ignores stickiness entirely is exactly the method that beats it.
The whole idea, drawn. Carbon asks whether something will stick to it; a membrane asks only whether it fits. Water fits. Nitrate does not, and is carried away rather than held.
I think that is rather elegant. The property that makes nitrate invisible to carbon is the same property that makes it irrelevant to a membrane.
What that looks like in practice
Reverse osmosis for drinking water is a well-established, independently certified category. There is a standard written specifically for it — NSF/ANSI 58 — and nitrate and nitrite reduction is one of the claims a system can be certified against and tested for. That matters more than any manufacturer's brochure: it means an independent laboratory has checked that a given system does what it says on this specific contaminant.
If nitrate is the reason you are looking, that is the certification to look for by name.
Two honest notes, because you should know them going in. An RO system sends some water to the drain in the course of separating what you drink from what you don't — that is the mechanism working, not waste in the careless sense, and newer systems are markedly more efficient than older ones. And the membrane and pre-filters need changing on a schedule, the way any working thing does.
In return you get something quietly remarkable: a tap in your own kitchen producing water with the dissolved load stripped out, for nitrate and for a long list of other things at the same time. Not a boil, not a hope, not a pitcher that was never designed for the job. A physical barrier, independently tested, doing one thing extremely well.
What I take from this
Nitrate is unusual among water questions because it is so completely knowable.
You cannot taste it — but you can measure it, cheaply, and the state extension service will tell you exactly how often. You cannot boil it away — but you do not need to, because something else removes it properly. It matters most for a specific group of households, and those households can find out where they stand for the cost of a test.
That is not a frightening story. That is a solved one. And I find there is a particular kind of calm in knowing precisely what is in your water, precisely what it means, and precisely what to do about it — rather than wondering.
If you are on a well and there is a baby in the house, test. If you are on city water, your utility has already tested and will tell you.
And if the number comes back high, know this: it is one of the few problems in water with an answer this clean.
A pipe let go in Pueblo, Colorado, on the twenty-seventh of August.
What came out of it was raw sewage. Not treated, not partly treated. Untreated wastewater, straight out of the city's own wastewater department, into the Arkansas River. Four point two million gallons of it.
Put that number somewhere you can hold it. A backyard swimming pool takes about twenty thousand gallons. This was two hundred pools. Of sewage. Into a river.
What the state did, and did quickly
Colorado moved. The Department of Public Health and Environment put an advisory on the river from where Fountain Creek joins it down as far as John Martin Reservoir, naming the towns along the way: Blende, Avondale, Fowler, Manzanola, Rocky Ford, La Junta, Las Animas. Stay out of the water. Keep the children out. Keep the dogs and the livestock out. No swimming, no tubing, no fishing.
By the second of September, Parks and Wildlife had widened it to twelve more places — wildlife areas, a fish hatchery, ponds, a state park.
The Department of Agriculture went to the produce growers, because the Arkansas is irrigation water down there, and irrigation water that touches a cantaloupe is a food safety question under federal rule.
Nicole Rowan, who runs water quality for the state health department, put it plainly enough: "Right now, we're really concerned with recreating in the water."
Elevated E. coli downstream. Sampling ongoing, results posted as they come.
And the drinking water was fine
This part matters, and it is true. The state's line is that it has "no evidence that this spill impacted public drinking water systems."
Mike Hart, the city manager in La Junta, explained why to anyone who asked: "There's all sorts of different levels that it has to go through and treatments that it has to go through before it even makes it in to the system."
He is right. That is exactly how it is supposed to work. A town on a river does not drink the river. It drinks what comes out the far end of a treatment plant, and a treatment plant is a stack of barriers — screening, settling, filtration, disinfection — each one there because the one before it might not be enough.
Hold onto that thought, because there is something uncomfortable sitting inside it.
The thing that failed was a treatment plant
The four million gallons did not come from a factory or a farm or a storm drain. They came out of the City of Pueblo Wastewater Department. The facility whose entire purpose is to stand between a city's sewage and a river.
It is a building full of pumps and pipes and valves, run by people, and on the twenty-seventh of August a piece of it gave way.
That is not an indictment of Pueblo. It is the nature of the thing. Every barrier in the chain is a machine, machines fail, and the whole design philosophy of water treatment is built on that assumption. You do not use one barrier. You use several, because you expect to lose one.
Now look at the map
The orange stretch is the public health advisory: Pueblo down to John Martin Reservoir, about a hundred and fifty miles. The blue is the rest of the same river — across Kansas, into Oklahoma, and through the middle of Tulsa. Nobody along the blue was notified, because there is no mechanism that carries a state advisory across a state line with the water it describes.
The advisory runs from Fountain Creek to John Martin Reservoir. Roughly a hundred and fifty miles of eastern Colorado. Past that point, officially, the story ends.
The river does not end. It crosses into Kansas. It runs the width of that state. It comes into Oklahoma, past Kaw Lake and Ponca City, and then it runs straight through the middle of Tulsa — under the bridges, past the trail, through the part of town people take their children to on a Saturday.
Nobody in Kansas was notified because nobody had to be. Nobody in Oklahoma was told a thing. There is no mechanism that carries a state health advisory across a state line with the water it describes. The advisory is a jurisdiction. The river is a river.
By the time anything from Pueblo could reach Oklahoma it would be diluted by hundreds of miles of flow, by tributaries, by a reservoir, by time. Almost certainly to nothing. That is the honest answer and it is a reassuring one.
It is also an answer nobody in Oklahoma was given, because nobody in Oklahoma was asked.
What this is not
Let us be careful, because this is where an article like this usually goes wrong.
This spill did not touch your tap water in Tulsa. Tulsa does not drink the Arkansas. Its water comes from Lakes Spavinaw and Eucha out on Spavinaw Creek, and from Oologah on the Verdigris, treated at the Mohawk and A.B. Jewell plants. Broken Arrow treats Verdigris water. Sand Springs takes from Skiatook Lake. Not one of the systems across this metro draws from the Arkansas.
Anybody telling you that four million gallons of Colorado sewage ended up in your kitchen is selling you something. It did not.
What it is
It is a demonstration, carried out in public, of three things that are true about every river-fed water system in the country.
Your water is only as clean as everything upstream of it. And upstream is longer than anybody pictures. It is not the stretch you can see from the bridge. It is every mile, every town, every farm, every plant, every pipe, all the way back to the headwaters, in states you have never driven through, run by people you will never meet.
The barriers between that and your glass are machines. Well built, well run, mostly. Not permanent. The Pueblo plant proves it: the failure in this story happened at a treatment facility, not despite one.
And you will not always be told. Not because anyone is hiding anything — Colorado was fast and open about this, dashboards and all — but because the notification systems are drawn around jurisdictions and the water is not. What reaches you depends on whether someone with authority over your particular stretch of river decided you needed to know.
The people with no barrier at all
There is one group in this story worth singling out. Colorado's guidance included a line for private well owners near the river, telling them to seek advice from the water quality division.
A private well has no treatment plant. No screening, no settling, no disinfection, no compliance monitoring, no annual report landing in the mailbox. There is the ground, and there is a pump, and there is a tap. Whatever the aquifer is doing, the household drinks.
In Oklahoma, where a great many rural households are on their own wells, nobody would have been told anything at all — because the advisory would never have crossed the state line to reach them.
The last barrier
Every barrier in a water system belongs to somebody else. The watershed belongs to whoever farms it. The reservoir belongs to the utility. The treatment plant belongs to the city. The distribution main belongs to the district. Each one is maintained by people doing their best with the budget they have, and each one is a machine that can fail on a Thursday in August.
There is exactly one barrier in the chain that belongs to you, and it is the one at the end, in your own house, after the water has finished travelling through everybody else's.
That is not an argument about this spill. Four million gallons of Pueblo's sewage is not coming to Oklahoma.
It is an argument about what the spill shows: that the distance between a river and a drinking glass is a series of barriers held together by other people's maintenance schedules and other people's jurisdictions — and that the only one you control is the last one.
Colorado did this right. They found it, they said so, they published the numbers, they widened the advisory when the sampling told them to. That is a state agency working properly, and the people downstream of Pueblo were well served by it.
The question worth sitting with is not whether Colorado handled it. It is how far downstream "downstream" is assumed to reach — and what you would want standing between you and the water if the answer turned out to be "not as far as your house."
The calls started coming in around the middle of September. Twenty-six of them in eight days, by the city's own count. The complaint was the same one every time: the water smelled wrong. Earthy. Musty. One resident told FOX23 it reminded her of sewage, and that she had switched to bottled water.
Broken Arrow's answer was quick, and it was the correct one. The water is safe. There is no boil advisory. Every required test is passing. Utilities Director Timothy Robins pointed at the Verdigris River, the city's raw water source, and at a summer that would not end: "This aromatic that we're talking about that's earthy or some [have] reported as musty, this is a direct correlation to this hot extended heat season."
All of that is true. It is also, on its own, an incomplete account of what happened — not because anyone is hiding anything, but because the vocabulary available to a utility in this situation is unusually narrow. "Safe" is a word with a precise legal meaning in drinking water, and it is doing more work here than most people realise.
The August 2018 episode and the September 2026 episode, as described by the City of Broken Arrow at the time. Same river, same cause, same reassurance, same fix.
What people were actually tasting
The city's testing identified elevated 2-methylisoborneol, universally shortened to MIB. It is an organic compound produced by cyanobacteria and by certain soil bacteria, and it has a close cousin called geosmin — the compound responsible for the smell of rain hitting dry ground. Neither is a contaminant in any meaningful toxicological sense. Both are, however, among the most detectable substances a human being encounters.
The human nose registers MIB and geosmin at around five nanograms per litre. Five parts per trillion. To put five parts per trillion into a swimming pool you would need roughly a teaspoon of the stuff spread evenly through four hundred Olympic pools. People taste it. Instruments need a gas chromatograph to find it.
That gap between what a nose can detect and what matters to health is the whole story of an event like this. Residents were not imagining anything, and they were not being oversensitive. They were detecting something genuinely present, at a concentration where being able to detect it is the remarkable part.
The word "safe" is doing specific work
Drinking water in the United States is governed by two different sets of standards, and only one of them is law.
The National Primary Drinking Water Regulations are enforceable. They cover the things that can hurt you — lead, coliform bacteria, disinfection byproducts, arsenic, nitrate — and a utility that breaches them is in violation and must say so.
The National Secondary Drinking Water Regulations cover taste, odour, colour and staining. The EPA's own language could not be plainer: "EPA does not enforce these 'secondary maximum contaminant levels'." They exist "as guidelines to assist public water systems in managing their drinking water for aesthetic considerations." There is a secondary standard for odour — 3 on the threshold odour number scale — and no utility in America can be penalised for exceeding it.
So when Broken Arrow said the water was safe, the statement was accurate and the framework behind it was the enforceable one. What the statement does not address, because no regulation requires it to, is the aesthetic complaint itself. There is no violation to report, no deadline to meet, and no public notice to issue. The only pressure a utility faces on taste and odour is the phone ringing.
This has happened before, in almost identical terms
In August 2018, Broken Arrow residents reported the same musty water. City spokeswoman Krista Flasch said then: "We are not under a boil advisory. The water is safe to drink. The taste and odor issues are being caused by algae in the Verdigris River, which is the city's main source of raw water." The city increased pre-treatment and flushed the lines. Residents were told to expect improvement in a few days.
Eight years later the river is the same, the cause is the same, the reassurance is the same and the fix is the same. Utilities Director Robins made the point himself this month, noting that taste-and-odour events are common across Oklahoma during extended heat.
That is not an accusation. It is a description of a structural condition. A city drawing surface water from a river in a state that now routinely runs over a hundred degrees for weeks will get algal blooms, and blooms produce MIB. What recurs is not a failure; it is a characteristic. The question worth asking is not why it happened, but whether a recurring, predictable condition is being managed as one.
The number nobody published
Here is what is missing from the public record of this event: a number.
The city said MIB was elevated. It did not say to what. Across the local coverage — FOX23, News On 6, KJRH, the Tulsa World — there is no concentration figure, no trend, no indication of what "elevated" meant in nanograms per litre or how it compared to 2018. The city reported sampling at 35 locations across the distribution system and finding no broader water-quality problems, which is a meaningful statement about the regulated contaminants. It is not a statement about MIB.
No rule was broken by leaving the number out. Utilities are not required to monitor MIB, not required to report it, and not required to include it in the annual Consumer Confidence Report that lands in mailboxes each summer. The compound is unregulated, which means it is also largely undocumented in public. A resident who wanted to know how bad it actually got, or whether this September was worse than the last one, has no published series to consult.
The part that is a health question
MIB is not toxic. The organisms that often produce it can be.
Cyanobacteria — the blue-green algae behind most freshwater blooms — include species capable of producing cyanotoxins, of which microcystin is the best known. The EPA has issued ten-day drinking water health advisories: 0.3 micrograms per litre of microcystins for bottle-fed infants and pre-school children, 1.6 for school-age children and adults. Those advisories are also, in the EPA's words, "not regulations and should not be construed as legally enforceable federal standards."
The tempting inference — smell means toxins — is wrong, and so is its opposite. A USGS study of Cheney Reservoir in Kansas tracked both over fifteen years and found the relationship runs one way only: "Taste-and-odor compounds, therefore, may be used as indicators that microcystin may be present; however, microcystin was present without taste-and-odor compounds, so taste or odor alone does not provide sufficient warning to ensure human-health protection."
Read that carefully, because it is the opposite of reassuring in a way most coverage misses. The odour is not evidence of toxins. But the absence of odour is not evidence of their absence either. A nose is a superb instrument for detecting MIB and a useless one for detecting microcystin. Nothing in the Broken Arrow reporting suggests cyanotoxins were detected, and nothing in it suggests anyone was asked.
What a resident can reasonably do
Not much of this is actionable at the level of an individual household, and it is worth being honest about that rather than pretending otherwise.
Reporting the problem to the utility directly does matter, and Broken Arrow made the point explicitly this month: staff do not monitor social media, and a complaint posted to Facebook is not a complaint received. The city's own count of 26 calls is the entire dataset it has on how widespread the taste was. A resident who posts about it instead of calling has removed themselves from the record.
Beyond that, the useful questions are the ones that ask for numbers rather than assurances. What was the MIB concentration, and at which sampling points? How did it compare with previous events? Is the city monitoring for cyanotoxins during blooms, and if so, what did those tests show? None of these are gotcha questions. All of them have answers that a utility either has or does not have, and finding out which is the point.
Chilling water in a covered jug in the refrigerator genuinely reduces the perception of MIB, because volatile compounds are less noticeable cold. That is a comfort measure, not a treatment, and it should be described as one.
The honest summary
Broken Arrow's water met every enforceable standard throughout this event, as far as the public record shows. Residents were not wrong about what they smelled. Both of those statements are true at once, and the gap between them is not a scandal — it is the regulatory architecture working exactly as designed, in a situation it was not designed for.
What the architecture does not provide is a number in public, a trend across years, or any requirement to look for the one thing in a bloom that would actually be a health matter. Those gaps are not Broken Arrow's invention. They are national, and they show up every time a hot summer meets a river.
Turn on your kitchen tap in Tulsa and some of what comes out started as rain on a pasture two counties away.
Tulsa draws raw water from two directions. Lake Spavinaw and Lake Eucha sit about fifty miles northeast on Spavinaw Creek, across Mayes and Delaware counties. Lake Oologah sits north, on the Verdigris. The Mohawk plant runs on Spavinaw and Oologah water; the larger A.B. Jewell plant runs on Oologah. So the honest version is that a good share of Tulsa’s supply comes down out of poultry country — not all of it, and which plant serves your address depends on where you live.
Either way the principle holds. Before it was lake water it was rain, and before that it was rain landing on pasture, on fields, on farmland. Whatever is on that ground when it rains goes where the water goes. Which is to say: to you.
This is the part of water quality nobody puts on a label. Your utility can only treat what arrives. What arrives depends on a watershed you have never driven through, and on decisions made by people you will never meet.
The chain the City of Tulsa describes on its own water FAQ: litter on the ground, phosphorus in the runoff, algae in the lake, geosmin in the glass.
The advocacy version, and the boring version
If you go looking for this topic online you will land on the Environmental Working Group, which reported that about sixty million Americans get water from large systems where nitrate was detected at or above 3 milligrams per litre between 2017 and 2019. Read that carefully. Three milligrams is EWG’s own indicator for “elevated”; the federal limit is 10. EWG is an advocacy non-profit and it measures against thresholds it sets itself, which is why its maps look more alarming than your utility’s report. A 2009 George Mason University survey of 937 members of the Society of Toxicology found 79 percent thought EWG overstated chemical risks.
There is no need for that framing here, because the Oklahoma version of this story is already on the public record. It is duller, and it is worse.
Twenty-one years in federal court
In 2001 the City of Tulsa sued Tyson Foods and five other poultry companies. The claim was straightforward: growers were spreading poultry litter — manure and bedding — on land in the Eucha and Spavinaw watershed. The phosphorus in it ran into the lakes. The phosphorus fed algae. The algae wrecked the taste of Tulsa’s drinking water. As the court recorded it, Tulsa alleged its supply had been affected by an increase in phosphorus “which has in turn resulted in excessive algae growth.” That was the city’s allegation rather than a finding of fact — the case settled in 2003, before anyone had to prove it.
Then the State of Oklahoma sued the same industry in 2005 over the neighbouring Illinois River watershed. That case took twenty-one years.
It went to trial. It sat. In June 2025 Judge Gregory Frizzell ruled that conditions in the watershed “have not materially changed since trial.” In December 2025 he entered judgment: poultry waste was “the principal contributor of the phosphorus causing injuries,” Lake Tenkiller had “become eutrophic,” the continuing injury amounted to irreparable harm, and the companies were placed under a thirty-year remediation order across a watershed of about 1,069,530 acres.
Four of the six companies settled in early 2026. Frizzell threw those settlements out on 8 April, finding the money would not cover a thirty-year problem and that once the funds ran dry “it appears likely that Oklahoma taxpayers would be paying the special master’s fees and expenses.”
On 13 July 2026 the Attorney General announced a global settlement covering all six: nearly $44 million, of which $41,671,000 goes to an Environmental Relief Fund, $420,000 to penalties and $1.9 million to an independent compliance monitor. Land application of litter is capped at 40 percent of litter removed in years one and two, 30 percent in years three and four, and 20 percent in years five through seven. Note what those caps govern — a share of litter, not a tonnage. Frizzell himself asked at a hearing whether application could still rise if bird numbers grew.
And it is not finished. The Tenth Circuit stayed the December judgment in August 2026 and sent the matter back to the district court, which has not yet approved the settlement. Twenty-one years in, the question of where the manure goes is still open.
What you actually taste
Here is the part that connects to your kitchen, and Tulsa says it themselves. From the city's own water FAQ: chicken litter runoff brings phosphorus, phosphorus “acts like a fertilizer so when it gets into the lakes it causes algae blooms,” and when the algae dies it produces geosmin. “Geosmin gives the water a musty smell and taste.”
That earthy, dirt-after-rain flavour some summers? That is the farm, arriving. It is the same compound that makes beets taste like beets.
Two things are true about geosmin and both matter. It is not dangerous — the USGS calls these compounds nuisance constituents rather than health hazards, and there is no federal limit on them. And your nose is absurdly good at finding it. Detection starts around ten nanograms per litre, which is roughly ten parts per trillion. You can taste it at concentrations nobody would bother regulating.
So an earthy taste is not by itself evidence that anything is unsafe — geosmin is a nuisance compound, not a toxic one. That is a statement about geosmin, though, not a clean bill of health for your water, and nobody can give you one of those from a description of a taste. Tulsa filters through sand and granular activated carbon, which the city says removes taste and odour from organic material in the source water. Carbon is the accepted treatment for taste and odour compounds, and taste and odour reduction is the class of claim NSF/ANSI 42 covers.
Nitrate is the serious one
Phosphorus ruins the taste. Nitrate is the one with a health limit behind it.
The federal MCL is 10 milligrams per litre as nitrogen. Watch those last two words — a lab reporting nitrate as the ion rather than as nitrogen produces a number over four times larger, and people compare the wrong figures constantly. EPA's language is blunt about the risk: infants under six months drinking water above the limit “could become seriously ill and, if untreated, may die.” Blue baby syndrome. The toxicological profile from ATSDR, the federal agency that writes them, puts the highest risk on bottle-fed infants aged one to three months, because their stomach chemistry converts more nitrate to nitrite and the enzyme that repairs the damage is not fully online until about four months.
Oklahoma DEQ adds the detail that catches people out: boiling does not help. It concentrates it. “This contaminant cannot be removed or reduced by boiling; boiling will increase the concentration of nitrate in the water.”
Nitrate is also the clearest illustration of why “do I need to treat my water?” is a question that starts with a test rather than a catalogue. It is invisible. It has no taste. Boiling makes it worse rather than better. And the technologies that address it are well established — reverse osmosis is among the methods federal regulation recognises for nitrate. What you cannot do is judge it by looking at the glass, which is the whole argument for knowing your own numbers before you decide anything at all.
If you are on a well, this is your problem alone
City water gets tested constantly and published annually. Private wells get none of that. EPA is unambiguous: private wells are “not regulated by the Federal Government under the Safe Drinking Water Act nor by most state governments,” and “private well owners are responsible for delivering safe drinking water to their households.” Nobody is checking. There is no report coming.
And Oklahoma has the numbers to make that uncomfortable. The Oklahoma Water Resources Board sampled 741 wells across the state. 14.2 percent came back over the nitrate limit. In alluvial and terrace aquifers — the shallow ones, where most rural domestic wells are finished — it was 27 percent. Bedrock aquifers accounted for only 5 percent of the exceedances. EPA's modelling estimates that groundwater under about 12 percent of Oklahoma's land area sits above the nitrate limit.
Be careful with that 27 percent: it describes wells in a state monitoring network, not a survey of private household wells, so it indicates where the risk sits rather than predicting yours. The point stands anyway. Shallow wells in this state fail a limit written around infant safety often enough that guessing is not a strategy, and the only way to know which kind you have is to send a sample off.
EPA recommends testing a private well annually for total coliform bacteria, nitrate, total dissolved solids and pH. OSU Extension splits it differently: coliform bacteria every year, inorganic chemistry including nitrate every three to five years, or sooner if you suspect a problem. Either way it costs very little, and for a well owner it is money better spent than almost anything else.
One more figure from the city's own page
The same Tulsa FAQ publishes hardness by treatment plant: 8.2 grains per gallon at A.B. Jewell, 5.2 at Mohawk. Worth knowing, because hardness figures get quoted loosely in the water treatment trade, and the real ones are published by the utility for free.
What to do with all this
If you are on city water and the taste goes earthy in late summer, geosmin is the usual explanation, and activated carbon is the treatment class that addresses taste and odour. If you are on a well anywhere near row crops, pasture or a lagoon, get a nitrate test from a certified laboratory — and if you have an infant in the house, do it before you make up another bottle. A screening at the tap for pH and dissolved solids, whoever performs it, does not measure nitrate. That needs a laboratory.
And whenever a source puts an alarming figure in front of you, two questions resolve most of the disagreement in this subject: what threshold is it measured against, and who set that threshold.
This article is general information about watersheds, public water supplies and federal drinking water regulation. It is not medical advice. Contaminant levels vary by system, by well and by season; the figures here come from the published sources listed below and are not a statement about the water at your particular address. If nitrate is a concern in your home, have your water tested by a certified laboratory.
Almost every American drinks disinfected water, and almost nobody knows which disinfectant. There are two common ones. They behave differently, they leave different things behind, and the reason your utility chose one over the other is a federal rule most people have never heard of.
This is an attempt to explain both, plainly, including the part that gets exaggerated most often — what happens in the shower.
Two chemicals, one job
Chlorine is the older one. It is a strong disinfectant and it works fast, which is exactly why it does not last. It gets used up reacting with whatever it meets on the way to your house.
Chloramine is chlorine with ammonia added. The EPA describes it this way: “Chloramines are most commonly formed when ammonia is added to chlorine to treat drinking water,” and they “provide longer-lasting disinfection as the water moves through pipes to consumers.” The agency calls that role secondary disinfection. It is a weaker disinfectant that survives the trip.
The form utilities use is monochloramine, and it is not new — the EPA noted in 2009 that it had already been in use for more than ninety years, and that more than one in five Americans were drinking water treated with it.
Why so many utilities switched
Because of what chlorine leaves behind.
When chlorine meets the ordinary organic matter in a lake or a river — leaves, soil, algae — it forms new compounds. The two families that matter are trihalomethanes and haloacetic acids, abbreviated TTHM and HAA5 on a water report. They are byproducts of making the water safe, not contaminants that arrived in it.
The EPA set limits on them in the Stage 1 Disinfectants and Disinfection Byproducts Rule, published in December 1998, and tightened how they are measured in the Stage 2 rule, published in January 2006. The limits are 80 parts per billion for TTHM and 60 for HAA5.
Chloramine is less reactive, so it forms less of both. That is the whole reason for the switch. As the Water Research Foundation put it, utilities adopted chloramine “primarily to comply with the U.S. Environmental Protection Agency's Stage 1 and Stage 2 Disinfectants and Disinfection Byproducts Rules.”
The trade you may not have been told about
Chloramine produces less of what is regulated. It also produces more of some things that are not.
The EPA is unusually direct about this, and the wording is worth reading twice:
“Regulated disinfection byproducts are produced in lower amounts when monochloramine is used... Compared to chlorine, water treated with monochloramine may contain higher concentrations of unregulated disinfection byproducts but the cancer risk is unknown. There are few studies on health effects of unregulated disinfection byproducts.”
The best-known of those unregulated byproducts is NDMA, a nitrogen compound associated with chloramination. It has no federal limit. The EPA monitors it and several relatives. California, which moves faster than the federal government on these things, sets a notification level of 10 nanograms per litre — a level at which the utility must tell the state, not a level at which anyone is in danger.
And the list is not closed. In November 2024 a team including an EPA researcher published a paper in Science identifying chloronitramide anion, a previously unrecognised decomposition product of inorganic chloramines, in treated drinking water. Its toxicity has not been established. It had simply never been looked for.
None of this means chloraminated water is dangerous. It means the honest position is that one set of byproducts has been traded for another, and the second set is less studied. Both of those sentences are true at once.
The whole difference, drawn. Chlorine is two chlorine atoms. Monochloramine swaps one of them for nitrogen and two hydrogens — which is ammonia, bonded on. That single change is why one is stronger and the other lasts longer.
The limits, and what they actually are
Federal law sets a maximum residual disinfectant level — an MRDL — of 4.0 milligrams per litre for both chlorine and chloramine, measured as an annual average. That is 4 parts per million. The same number is also the health goal, which is unusual: for most contaminants the goal is lower than the limit.
Compliance is an average, not a single reading, which is why a water report shows a running annual average and a range. Tulsa's most recent report, for instance, gives a chloramine annual average of 2.5 ppm against the 4.0 limit, with readings between 1.6 and 3.2. Its TTHM figure is 39 ppb against a limit of 80, and its haloacetic acids 24 against 60.
Now the shower
Here is the claim you have probably seen: you absorb more from a ten-minute shower than from drinking the water all day. It is close to something real, and it is usually told wrong.
The research is genuine and it is old. In 1990, Jo, Weisel and Lioy published two papers in Risk Analysis measuring chloroform in the exhaled breath of people who had just showered. Their finding, in their own words: “The internal dose from showering (inhalation plus dermal) was comparable to estimates of the dose from daily water ingestion.”
The word is comparable. Their own numbers put a single ten-minute shower at a risk estimate of 1.22 × 10⁻⁴, and daily drinking between 0.130 and 1.80 × 10⁻⁴ depending on how much you drink. The shower estimate sits inside the drinking range. It is not larger. Anyone who tells you a shower is worse than drinking has rounded in a convenient direction.
A second paper by the same group found the dermal route — absorption through skin — contributed roughly as much as breathing did. And a controlled human study by Backer and colleagues in 2000, summarised by California's OEHHA, found that of people who drank a litre, showered for ten minutes, or bathed for ten minutes, “the highest levels of THMs were found in the blood samples from people who took 10-minute showers, whereas the lowest levels were found in the blood samples from people who drank 1 L of water.” That study had ten or eleven people per group. It is a real result and a small one.
The EPA has looked at this directly. Its 2006 report Exposures and Internal Doses of Trihalomethanes In Humans concluded that “the inhalation exposure pathway represents a significant contribution to THM internal doses.” So the route is recognised. It is not fringe.
But it is not the chloramine you are breathing
This is the part almost every article on the subject gets wrong, and it matters.
Monochloramine does not evaporate readily. The EPA states plainly that it is unlikely to cause inhalation problems because it “does not enter the air easily.” The compound steaming up your bathroom is not chloramine. It is chloroform and its relatives — the trihalomethanes — which are volatile and do leave the water.
Which leads somewhere slightly awkward for the people who sell this story hardest. Trihalomethanes are primarily a chlorination byproduct. Chloramine produces fewer of them. So if your utility uses chloramine, the shower-exposure research — which was conducted on chlorinated water — describes a smaller effect in your house, not a larger one.
The shower story is a chlorine story. It gets attached to chloramine because the two words sound alike.
What is not established, and who says so
People report skin irritation and breathing trouble after a utility switches to chloramine. The CDC investigated. According to the EPA's summary, that investigation “was unable to draw any conclusions about monochloramine use and health effects.” The EPA's own position on both questions is that water meeting the standard has “no known or anticipated adverse health effects, including breathing problems” — and the same sentence again for skin.
There is a specific confusion behind a lot of this. Swimming pools genuinely do produce an irritating chloramine. The CDC says so: chloramines in a pool “irritate skin, eyes, and the respiratory tract… when they turn into gas into the air above the water.” But that compound is trichloramine, formed when pool chlorine reacts with the sweat and urine swimmers bring in. It is a different molecule from the monochloramine dosed into a water main, formed by a different reaction, in a different place. The CDC's pool guidance does not mention drinking water at all.
If your eyes stung at the pool, that was real. It was not the same chemical.
Three things about chloramine that are genuinely documented
Dialysis. Chlorine and chloramine must be removed from water used in a dialysis machine, because that water contacts blood directly. The EPA is equally clear that dialysis patients can drink the same water without concern. Clinics handle this; patients do not need to.
Fish. Chloramine is toxic to fish, shellfish, reptiles and amphibians, which take it up through their gills straight into the bloodstream. Human digestion neutralises it first. Aquarium shops sell conditioners for exactly this reason, and unlike chlorine, chloramine will not simply gas off if you let a bucket stand overnight.
Old pipes. This is the serious one. Washington DC switched from chlorine to chloramine in November 2000, and lead levels in tap water rose sharply. The CDC's explanation is the clearest account available:
“In the mid-1990s in the District of Columbia, high levels of free chlorine were used to decrease coliform bacteria in water, a process that inadvertently changed the type of lead mineral coating in the water lines to one with very low solubility… When the free chlorine was replaced with chloramines, the transformed highly insoluble lead scale minerals were no longer stable and dissolved.”
Read carefully, that is not a story about chloramine being poisonous. It is a story about a protective crust inside old lead pipes that had formed under one water chemistry and dissolved under another. The CDC's own conclusion is the general lesson: “Changes in water treatment and disinfection practices can substantially undermine lead corrosion control.” The agency later acknowledged that its own 2004 report on the episode had been misleading about the effect on children's blood lead levels.
Chloramine did not create the lead. The lead pipes did. Changing the water chemistry without adjusting corrosion control is what let it loose.
How to find out which one you have
Every community water system in the country must send customers an annual report — a Consumer Confidence Report — and the EPA's rule is that it must arrive by July 1 each year. It is free, it is yours, and most people bin it.
In it, look for a row labelled Chlorine or Chloramine, measured in ppm against an MRDL of 4. Below it you will find Total Trihalomethanes in ppb against 80, and Haloacetic Acids against 60. That is the whole picture in three lines.
If you cannot find your copy, the EPA maintains a lookup at sdwis.epa.gov/fylccr. Enter your state, and optionally your county, and it will list the systems.
Whatever it says, it is better to know the name of the thing in your water than to guess at it.
This article is general information about municipal water treatment and public health guidance. It is not medical advice, and it does not describe, evaluate or recommend any treatment equipment. Water disinfection exists because the diseases it prevents killed people in large numbers, and every source quoted here treats disinfected water as safe to drink.
Two federal frameworks have opinions about copper touching things you consume, and they want opposite outcomes.
The FDA's Food Code says a copper mug must be lined before an acidic drink goes in it. The EPA's registration of antimicrobial copper says the metal must be bare, uncoated, no wax or paint, or the antibacterial effect does not count.
Both are right. They are regulating different things. Untangling that is a decent tour of what copper actually does — in a cup, and in the pipes behind your walls.
The Moscow mule problem
The FDA Food Code, section 4-101.14, says that copper and copper alloys such as brass “may not be used in contact with a FOOD that has a pH below 6” — and it names examples: vinegar, fruit juice, wine.
A Moscow mule is vodka, ginger beer and lime. It is served, by tradition, in a copper mug.
Iowa noticed. In July 2017 the state issued advisory bulletin AB-2017-01, Use of Copper Mugs in the Serving of Alcoholic Beverages, which observes drily that “the pH of a traditional Moscow Mule is well below 6.0.” The bulletin also gives the fix, which is the same fix most mugs already use: “Copper mugs lined on the interior with another metal, such as nickel or stainless steel, are allowed to be used.”
This is a food-service licensing rule. It governs bars and restaurants, not your kitchen cupboard. But the chemistry does not check who is pouring.
Somebody measured it
In early 2022 a team at Carroll College in Montana published in the Journal of Environmental Health the obvious experiment nobody had bothered to run: they put a simulated mule in a bare copper vessel and watched the copper come off.
The rate was 0.048 parts per million per minute at room temperature. At that pace the liquid passes 1.3 ppm — the EPA's action level for copper in drinking water — in a little over twenty-seven minutes. Left for twenty days, the concentration reached around 1,000 ppm.
Two honest caveats, because that number gets waved around. The EPA's 1.3 ppm figure is built for water you drink every day for a lifetime, not for a cocktail. And twenty days is a laboratory endpoint, not something anyone does. The authors' own recommendation is the modest one: line the mug, as the Food Code says.
The practical version: if your mug is lined — and almost all sold today are — there is nothing to think about. If it is bare copper inside, do not leave an acidic drink sitting in it.
Copper is a nutrient and a toxicant, and the gap is wide
Both of these come from the same agency, in the same document. The CDC's ATSDR says copper is essential: “It is essential for people to ingest small amounts of copper every day in food and water.” And a few lines later: “Ingesting a high amount of copper, usually in drinking water, can cause vomiting, nausea, abdominal pain, and/or diarrhea.”
The numbers give the scale. The NIH puts the recommended daily intake for adults at 900 micrograms, and the tolerable upper limit at 10,000 — a gap of about eleven times. The NIH also notes that most people get enough from food, with shellfish, nuts, seeds, organ meats, whole grains and chocolate the richest sources. Chocolate is a legitimate copper source. That is a free fact.
For the level where people actually notice something, the best evidence comes from a human drinking-water study summarised in ATSDR's toxicological profile. At 1 milligram per litre, one person in sixty reported stomach symptoms — fewer than in the control group. At 3 mg/L, ten did. At 5 mg/L, nine. The step change sits between 1 and 3.
Which makes the EPA's drinking water numbers easier to read. The action level for copper is 1.3 mg/L, at the 90th percentile of sampled taps. There is also a secondary standard — unenforced, purely aesthetic — of 1.0 mg/L, the point at which water starts to taste metallic and leave blue-green stains.
Notice the order. The taste threshold is below the health threshold. With copper, in most cases, you would taste or see a problem before you had one. Very few contaminants are that polite.
About the overnight copper bottle
There is a long-standing practice of storing drinking water in a copper vessel overnight, and a modern industry of copper bottles sold on the back of it.
The underlying chemistry is real. Copper ions kill bacteria on contact — the oligodynamic effect — and the EPA takes it seriously enough to have registered copper alloys as antimicrobial surfaces. The registered label claims copper “kills greater than 99.9% of Gram-negative and Gram-positive bacteria within 2 hours of exposure,” and in 2021 the EPA extended that to SARS-CoV-2.
Now read the rest of the same label. The registration covers “door handles, doorknobs, handrails, faucets, light switches, and countertops (non-food use only).” And in bold federal plain English: “Not approved for direct food contact or food packaging uses.”
So the document most often cited to prove copper cleans your water is a document that specifically excludes copper touching anything you eat or drink. It is about dry doorknobs.
As for the broader health claims — detoxification, joint health, immunity — in September 2020 the FTC sent a warning letter to a copper water bottle company over marketing including “drinking from a copper bottle can be a great way to stay free of the flu, cold and other illnesses” and “Did you know copper kills coronavirus?” The FTC's position is the standard one and applies to everyone: it is unlawful to advertise that a product can prevent, treat or cure disease “unless you possess competent and reliable scientific evidence.” The company was told to stop within forty-eight hours.
A copper bottle is a nice object. It is not a medical device, and no US authority treats it as one.
Copper water tube. Impermeable, non-combustible, and the default American plumbing metal for generations — until the price of it, and the people stealing it, changed the arithmetic.
The pipes, which is where copper earns its reputation
Copper has been the default American plumbing metal for generations, and the engineering case is real.
It does not burn. It stays ductile at temperatures no house will ever see. And — the property that matters most and gets discussed least — it is impermeable. An independent 2024 analysis put it plainly: copper “does not allow chemicals to pass through the pipe wall,” whereas gasoline, for example, can permeate polyethylene pipe, with benzene and toluene exceeding their federal limits inside the water “before the odor is even detected.” Copper pipe running through contaminated ground stays sealed. The same analysis put copper service line lifespans in the seventy-five to hundred-year range.
Now the other side, because it is well documented and rarely mentioned by anyone selling copper.
Pinhole leaks are real. Maryland convened a state task force on them in 2004 after suburban homeowners started losing ceilings. Its finding was refreshingly unsatisfying: “The specific causes for pinhole leaks in copper plumbing have yet to be determined,” and “it is widely believed that there is no one cause; and there is no one solution.” In one utility's service area, roughly 5,400 of 417,000 accounts had reported leaks — but concentrated hard by age: over 300 of every 1,000 houses built in the 1930s, against about 75 per 1,000 from the 1940s.
EPA researchers studying the same problem were blunter: copper pitting is “a significant problem at many water utilities across the United States,” and copper pinhole leaks “are widely under reported.”
Here is the counterintuitive bit. The folk explanation is that acidic water eats copper pipe. Both the Maryland task force and the EPA study point instead at high pH combined with low alkalinity as conditions associated with pitting. The chemistry is messier than the slogan.
So why is the new house down the road plumbed in plastic?
Not because copper stopped working.
HUD tracked the shift: PEX tubing held 10 percent of the US single-family new-construction plumbing market in 1997, 16 percent by 2002, and 63 percent by 2016. HUD's stated reasons are material and labour cost, the near-tripling of copper prices after 2004, and one that reads like a crime novel — thieves were stealing copper out of houses after it was installed but before they were occupied. HUD's observation: “PEX has no salvage value, thieves don't target it.”
Copper lost market share on economics and theft, not on performance. Most existing American housing stock is still plumbed with it.
Two things worth doing, whatever your pipes are made of
State health departments converge on the same advice, which is free and takes seconds.
Flush a line that has sat. Minnesota's health department: “Let the water run for at least 30-60 seconds before using it for drinking or cooking if the water has not been turned on in over six hours.” Water standing in copper pipe overnight picks up copper. Moving water does not.
Never draw drinking or cooking water from the hot tap. Same source: “Hot water releases more copper from pipes than cold water.” Massachusetts says the same. This is the single most useful and least known item on this page, and it applies to lead as well as copper. If you want hot water for cooking, take it cold and heat it.
And the mug, finally
The Moscow mule's origin is usually told as a single tidy story about a Los Angeles bar in 1941 and a meeting between a vodka man and a ginger beer man with too much stock. A version published in 1948 says roughly that. A version published in the Wall Street Journal in 2007 credits a bartender named Wes Price, who said he simply wanted to clear the cellar.
Both accounts are in print, they disagree, and there is no primary documentation settling it. The drink is older than the paperwork, which is true of most good drinks.
Drink it out of a lined mug.
This article is general information about materials, plumbing and public health guidance. It is not medical, dietary or plumbing advice, and it does not describe or evaluate any treatment equipment. If you are concerned about copper in your own water, your utility's annual report gives the system-wide figures, and a licensed plumber can tell you what your house is actually plumbed with.
Every discussion of drinking water quality stops at the property line. Your utility treats the water, tests it, publishes the results, and delivers it to a meter. What happens in the two hundred feet of pipe between that meter and your shower head is nobody’s job but yours — and it is the stretch where the most dangerous waterborne organism in the United States actually lives.
Plumbers call it premise plumbing. It is the part of the system that no treatment plant can reach, no annual report describes, and almost no homeowner thinks about. It is also, according to six years of CDC surveillance, where 87 percent of America’s drinking-water outbreaks now begin.
The utility's responsibility ends at the meter. Everything to the right of that line is unregulated, uninspected and unreported.
Water has an age
Treated water leaves a plant carrying a disinfectant residual — a small reserve of chlorine or chloramine intended to keep it safe on the journey. That reserve is consumed as it travels. It reacts with pipe walls, with sediment, with organic matter, and with time.
Water sitting still in a pipe is not preserved. It is aging. CDC’s guidance on building water systems is direct about what stagnation produces: “low or undetectable levels of disinfectant.” Once the residual is gone, the pipe is no longer a delivery system. It is a habitat.
What moves into that habitat is biofilm — a slime layer on the inside of the pipe that shelters organisms from whatever disinfectant is left. Legionella lives inside it, and in the right conditions it multiplies.
The window where it grows
CDC puts the growth range for Legionella at 77°F to 113°F. That is not an obscure band. It is the temperature of a hot water tank set economically, the temperature of a cold line running through a warm wall cavity in July, and the temperature of any hot water that has sat long enough to cool halfway.
The guidance that follows from it is specific. Cold water should be stored and circulated below 77°F. Hot water should be stored above 140°F and circulated at no less than 120°F. The aim is to keep water out of the window entirely, on both sides.
And here the advice runs into a wall.
The temperature that suppresses Legionella is the temperature that burns a child in about two seconds. Growth range and storage guidance from CDC; scald times from the American Society of Sanitary Engineering.
At 140°F — the temperature CDC says to store at — water causes a second-degree burn in roughly two seconds. At 131°F it takes about five seconds. At 120°F, around three minutes. Those figures come from the American Society of Sanitary Engineering, and they are why most water heaters leave the factory set to 120°F.
So the setting that protects a toddler from a scald sits barely above the top of that band — and hot water that has stood in a pipe long enough to cool drops straight back into it. ASSE names the problem plainly: “a direct conflict between the safe delivery temperature of hot water to the points of use and the hot water temperature needed to minimize the growth of Legionella bacteria.”
The resolution is not a compromise temperature. It is to stop treating storage and delivery as the same number. A thermostatic mixing valve blends stored hot water down to a safe temperature before it reaches the tap, which lets the tank sit at 140°F while the shower runs at something that will not injure anyone. Storage and delivery become two decisions instead of one.
Dead legs
The second problem is geometric rather than thermal.
A removed fixture leaves its branch behind. The rest of the plumbing works normally, which is why nobody finds these until a wall is open.
A dead leg is a length of pipe that no longer carries flow, or carries it so rarely that the water inside is effectively permanent. They are created by ordinary events: a fixture removed but its branch left capped, a bathroom added and later closed off, a laundry connection abandoned when the machine moved, an irrigation tie-in unused since the previous owner.
Nothing about a dead leg announces itself. The rest of the plumbing works normally. But that stub holds water that is never replaced, never re-dosed with disinfectant, and frequently sitting in the growth window — and it connects to the same system that feeds the fixtures you do use.
CDC’s practical instruction for buildings is to find them: “look for faucets or fixtures that aren’t used regularly and flush them to maintain water flow.” A guest bathroom used twice a year is functionally a dead leg with a tap on the end.
The house that sat empty
This is where the two problems compound.
A home unoccupied for a month is a system with no flow anywhere. Every line becomes a dead leg. The residual decays throughout. The water heater, if it was turned down or off, drifts into the growth range and stays there. By the time someone returns and turns on the shower, the first thing out of the head is aerosol from water that has been sitting warm and undisinfected for weeks — and inhaled aerosol, not swallowed water, is how Legionnaires’ disease is contracted.
Asked how long a building can sit before this matters, CDC declines to give a single number, and the refusal is informative. A “prolonged period” for Legionella “may be weeks or months depending on plumbing-specific factors, disinfectant residuals, water heater temperature set points, water usage patterns, and preexisting Legionella colonization.”
Read that list again. Every variable in it is a property of your building, not of your water supply. Two houses on the same street, fed identical water from the same main, can sit empty for the same month and come back in completely different condition.
What the guidance actually says to do
Store hot, deliver warmTank at 140°F, tempered down at the fixture by a mixing valve.
Run what nobody runsGuest baths and spare taps need flow, not just a working valve.
Flush after time awayEvery outlet, hot and cold, until the hot side reaches temperature.
CDC’s procedure for returning a water system to service after low use is to flush hot and cold through every point of use — every shower, every faucet — until the water has been fully replaced, running the hot side until it reaches its maximum and ideally at least 120°F at the tap. The guidance adds a detail worth noting: minimize splashing and aerosol while you do it, because the flush itself is an exposure.
The rest is maintenance rather than response. Keep the heater at 140°F and temper the delivery. Run the fixtures nobody uses. Know where your abandoned branches are, and if you are already opening a wall, cut them out rather than capping them.
The part nobody owns
There is something uncomfortable in the structure of all this. The water utility is regulated, monitored, and required to publish. The organisms that cause almost all of the deaths in national outbreak data are growing downstream of everything that regulation touches.
In hospitals and hotels the response has been formal — water management programs, documented temperature logs, defined responsibility. In houses there is no equivalent, no inspection, and no report. The variables that decide the outcome are a thermostat setting most people have never looked at, a pipe stub nobody remembers, and how long the place sat empty.
None of which is visible from the tap.
This article is general information about building water systems and public health guidance. It is not medical or plumbing advice, and it does not describe or evaluate any treatment equipment. Water heater temperature and scald protection involve real safety trade-offs — particularly in homes with young children or older adults — and are worth discussing with a licensed plumber who can see your actual system.
Most people meet water hardness on a shower door. A white film that will not wipe off, spots that come back a day after the glass was cleaned, a kettle with a crust in the bottom of it. It looks like a cleaning failure. It is not. It is rock.
What it actually is, how much of it Tulsa has, and what can honestly be done about it are four separate questions, and the answers are less dramatic and more interesting than the advertising on either side suggests.
Hardness is dissolved rock, and it is measured in two units
Rain is soft. It picks up hardness on the way to you, by moving through ground that contains calcium and magnesium — limestone, chalk, dolomite — and dissolving a little of each. By the time the water reaches a treatment plant it is carrying those two metals in solution, and no amount of chlorination or filtration at the plant takes them out, because nobody is trying to.
It gets reported two ways, which is the first thing that confuses people. Milligrams per litre as calcium carbonate is the scientific unit. Grains per gallon is the plumbing-trade unit. One grain per gallon is 17.1 mg/L. Any time two sources appear to disagree wildly about your water, check whether one of them is quoting grains.
The US Geological Survey sorts the result into four bands:
Tulsa’s two treatment plants sit in different bands on the USGS scale. Figures from the City of Tulsa; classification from the US Geological Survey.
Tulsa has two answers, and yours depends on your address
The City of Tulsa publishes hardness per plant, and the two numbers are not close. A.B. Jewell runs 8.2 grains per gallon, or 140 parts per million. Mohawk runs 5.2 grains, or 89.
Put those on the USGS scale and they land in different categories. Jewell water is hard. Mohawk water is moderately hard — the band below. Same city, same utility, same bill, and a difference of 51 mg/L depending on which plant your street is fed from.
This is worth knowing before anyone quotes you anything, because a great deal of what gets said about Tulsa water is said about a city-wide average that does not exist. If a salesman tells you your water is hard, the reasonable question is which plant serves you, and the better one is what the number is at your own tap rather than at the plant. Hardness does not change much in the pipes, but your house may be on a blend.
It is not a health problem, and no regulator treats it as one
Worth saying plainly, because the marketing around hardness often implies otherwise: the EPA does not regulate it. There is no maximum contaminant level for hardness. It is not on the primary list, which covers things that can make you ill, and it is not on the secondary list either — the fifteen nuisance substances covering aluminium, chloride, colour, copper, corrosivity, fluoride, foaming agents, iron, manganese, odour, pH, silver, sulphate, total dissolved solids and zinc. Hardness appears in that document only as a side effect of total dissolved solids.
And the secondary standards are not enforceable anyway. The EPA describes them as “non-mandatory water quality standards” and says directly that it does not enforce them; they exist to help utilities manage the aesthetic side of what they deliver.
Calcium and magnesium are nutrients. Nobody is harmed by drinking them at these concentrations, and the water in a glass is fine. Hardness is an equipment and housekeeping question, not a safety one, and anyone selling it to you as a safety one is telling you something the federal government does not.
The study everyone quotes, and what it actually tested
There is one piece of research behind nearly every claim you will read about hard water and appliances. In 2009 the Battelle Memorial Institute ran a controlled study on water heaters, showerheads and fixtures, and the findings are genuinely striking:
Gas storage water heaters lost up to 24% of their efficiency over a simulated fifteen-year life on hard water, while the units fed softened water held their factory efficiency throughout. Tankless water heaters failed completely at 1.6 years of equivalent service, plugged solid with scale. Showerheads lost 75% of their flow in under eighteen months, and faucet strainers were close to fully blocked after nineteen equivalent days of use.
Those numbers get quoted constantly, and they are real. Two things rarely get quoted alongside them.
The first is the water. The heaters were tested at 30 grains per gallon and the tankless units at 26. Tulsa’s harder plant delivers 8.2. The study was run on water roughly three to four times harder than anything coming out of a Tulsa main, and the failures it produced are the failures of that water, not of yours.
The second is who paid for it. The study was commissioned by the Water Quality Research Foundation, which is the research arm of the Water Quality Association — the trade body for the industry that sells water softeners. That does not make the findings wrong. Battelle is a serious laboratory and the work was done properly. It does mean the questions asked were the questions a softener industry wanted answered, and it is the kind of thing a reader deserves to be told rather than left to discover.
What survives both caveats is the mechanism, and the mechanism is the part that matters. Scale forms when hard water is heated, because calcium carbonate becomes less soluble as temperature rises — which is why the crust turns up in the kettle, the heater and the dishwasher rather than in the cold line. That happens at 8 grains exactly as it happens at 30. It happens more slowly, in proportion to how much calcium is going past. Battelle’s own rate figure is about four percent of efficiency lost per five grains of hardness; carry that down to Tulsa’s 8.2 and you get something in the region of six or seven percent across fifteen years. That is our arithmetic on their number, not their finding, and it is worth about what any extrapolation is worth. But it is the right order of magnitude, and it is not nothing on a water heater you expected to run for fifteen years.
Two ways to deal with it, and they are not the same thing
This is where most of the confusion lives, because both approaches get sold under the word “treatment” and they do completely different jobs.
Removal takes the calcium out of the house. Sequestration leaves it in the water and stops it sticking. Only one of them softens.
Removal is ion exchange, which is what a water softener does. Water passes through a bed of resin that holds sodium; the resin swaps its sodium for the calcium and magnesium going past, and the water that comes out the other side genuinely has the hardness taken out of it. That is the only approach that ends the shower-door problem, because the shower door is calcium drying on glass and there is no calcium left to dry.
It costs something to do that. A softener needs salt, a drain connection, electricity, and a periodic regeneration cycle that flushes the captured hardness away and refills the resin with sodium. It puts that sodium into your water in place of the calcium — a small amount, proportional to how hard the water was, and worth knowing about if anyone in the house is counting it. And a proportion of municipal water goes down the drain every time it regenerates.
Sequestration is a different idea entirely. A food-grade polyphosphate is dosed into the water, and it wraps the calcium and magnesium in soluble complexes so they stay dissolved and travel on through the house rather than coming out of solution on a heating element. Nothing is removed. The hardness leaves with the water.
What makes it practical is an effect worth understanding, because it sounds too good on the face of it. Fully binding 200 ppm of hardness would stoichiometrically take around 500 ppm of sodium hexametaphosphate — an absurd dose. In practice two to four parts per million does the job, because the polyphosphate does not need to wrap every ion; it only needs to interfere with the first crystals as they try to form. Scale needs a seed to grow on, and a tiny dose is enough to stop the seed. The trade calls it threshold treatment, and it is why a cartridge the size of a forearm can protect a whole house.
The honest limits: it does not soften. Your water still has every bit of its hardness in it, soap will behave the way it always has, and the glass door will still need a squeegee. And polyphosphate hydrolyses faster as water gets hotter, so it is a protection that works best before and up to the heater rather than deep inside a tank that runs very hot.
What it does protect is the part you cannot see and cannot clean — the inside of the pipework, the heating element, the valves in a dishwasher and a washing machine, the narrow passages where a tankless heater actually fails. It does that with no salt to carry, no drain to plumb, no power, no regeneration cycle, no water sent down the drain, and no sodium added to what you drink. On line pressure alone, it keeps working through a power cut.
So what should you actually do
Find out which plant serves you, because that is a 51 mg/L question and it is free to answer. Then measure at your own tap rather than reasoning from the plant figure.
If the number comes back in the very hard band — which happens on private wells around here far more than on city water — removal is the honest answer and sequestration will not do what you want. If it comes back where Tulsa’s city water sits, the question is narrower and more useful: you are not trying to rescue a system from 30-grain water, you are trying to keep a moderate, steady calcium load from quietly costing you efficiency on a heater over fifteen years. That is a protection problem rather than a rescue, and it is proportionate to treat it as one.
Either way, the spots on the glass are cosmetic and reversible. Scale on a heating element is neither. If you only deal with one of the two, deal with the one you cannot see.
This article is general information about water chemistry and public data. It is not plumbing advice. Hardness figures are the City of Tulsa’s own published values by treatment plant and can change; the classification bands are the US Geological Survey’s. The fifteen-year efficiency figure derived from the Battelle rate is our arithmetic applied to Tulsa’s hardness, not a finding of that study.
In the spring of 1993, pharmacies across Milwaukee ran out of anti-diarrheal medicine. Absenteeism climbed at the city’s hospitals and schools. It took health officials days to work out what they were looking at, because the thing making people ill was arriving through a system that was, by every measure then in use, working.
Roughly 400,000 people fell ill. At least 69 died, most of them people living with AIDS. The cause was Cryptosporidium, a parasite that had passed through the filters at the city’s southern treatment plant. The water had been treated. It had been chlorinated. And none of that mattered, because chlorine does not kill Cryptosporidium.
Milwaukee remains the largest documented waterborne outbreak in United States history, and more than thirty years on it is still the clearest illustration of something most people find counterintuitive: the two organisms that matter most in drinking water are the two that ordinary disinfection does not reach.
The parasite that survives the chlorine
Part of what makes Cryptosporidium difficult is a matter of packaging. The parasite spends part of its life cycle sealed inside an oocyst — a thick-walled capsule between four and six micrometers across, spherical to oval, tough enough to survive conditions that would destroy a bacterium.
The Environmental Protection Agency’s health advisory on the organism is blunt about the consequence. Ozone is the most effective chemical disinfectant against it, with chlorine dioxide second. Conventional chlorination is not reliable. The Centers for Disease Control and Prevention puts it more plainly still: Cryptosporidium is “poorly inactivated by chlorine or iodine disinfection.”
It also does not take much. In human challenge studies cited by the EPA, 62 percent of subjects given thirty or more oocysts became infected. The dose that infected half of healthy adults worked out at roughly 132 oocysts — but that figure varied enormously between strains, from as few as 9 to as many as 1,042 depending on the isolate. A handful of organisms, in the wrong strain, is enough.
Because the chemistry does not work, the control has to be physical. Under the Interim Enhanced Surface Water Treatment Rule, filtered systems must achieve at least 2-log removal of Cryptosporidium — that is, 99 percent. It is worth sitting with the EPA’s own description of what good practice delivers: “a well-operated water filtration system is capable of removing at least 99 of 100 Cryptosporidium oocysts.”
That is an engineering tolerance, not a guarantee. Ninety-nine percent removal of a large number is still a number. Giardia, which also forms cysts and also tolerates chlorine far better than bacteria do, presents the same basic problem in a slightly more forgiving form.
What actually puts Americans in hospital
Here is where the intuition breaks down.
The CDC’s surveillance summary of drinking-water outbreaks covering 2015 through 2020 — the most recent full accounting — recorded 214 outbreaks across 28 states, causing 2,140 illnesses, 563 hospitalizations and 88 deaths.
Of those 214 outbreaks, 187 were biofilm-associated: organisms growing inside plumbing rather than arriving from the source. One hundred and eighty-four of them were Legionella. Only 24 outbreaks — 11 percent — were the enteric illnesses most people picture when they think of contaminated water: norovirus, Shigella, Giardia, Campylobacter, Cryptosporidium, E. coli.
Now look at who got hurt. Those 24 enteric outbreaks produced 1,299 cases — 61 percent of all illness in the period — but only 10 hospitalizations and no deaths at all. Legionella produced 786 cases, a little over a third of the total, and from that smaller number came 544 hospitalizations and 86 deaths: 97 percent of all hospitalizations and 98 percent of all deaths in six years of national surveillance.
The organisms that make the most people ill and the organisms that kill people are not the same organisms.
The hazard that grows after the treatment plant
Legionella is not a source-water failure. It is a building problem. The bacterium establishes itself in premise plumbing — the pipes, tanks, and fixtures downstream of the water main — where it shelters inside biofilm and multiplies in water that has sat warm for too long.
The contributing factors CDC recorded read like a maintenance audit rather than a treatment failure: Legionella already present in a building’s water system, temperature and disinfectant conditions that favor growth, water sitting at or above 86°F, and aging plumbing. By the time water has traveled through a large building, the disinfectant residual that protected it in the main has often decayed to nothing.
That is why the outbreaks cluster where they do. Hospitals, long-term care and assisted living accounted for 113 outbreaks — 53 percent of the total — and within them 372 hospitalizations and 75 deaths, which is 85 percent of all deaths recorded. Hotels and lodges accounted for another 35. These are buildings with long pipe runs, large hot water systems, low-flow guest rooms that sit unused, and populations who are already unwell.
There is one detail in that surveillance period worth noting for what it may signal. For the first time, Legionella was reported in three outbreaks traced to private residences, in 2015 and 2019.
Why you cannot drink your way into Legionnaires’ disease
This is the most widely misunderstood fact about the most lethal organism in American drinking water: you do not catch Legionnaires’ disease by drinking contaminated water. You catch it by breathing it — inhaling aerosolized droplets small enough to reach the lungs. Showers, cooling towers, decorative fountains, hot tubs and misters are the exposure routes that matter.
It follows that a boil-water notice, which is aimed squarely at organisms you swallow, does very little about Legionella. It is worth understanding what such a notice actually buys you. CDC guidance during a boil advisory is a rolling boil for one minute, extended to three minutes above 6,562 feet. Boiling does handle Cryptosporidium, which is precisely why it is the advice given when a treatment barrier has failed — heat succeeds where the chlorine could not.
Where boiling is impractical, CDC points to filters certified under NSF/ANSI Standard 53 or 58 for cyst removal or cyst reduction, to an absolute one-micron filter, or to reverse osmosis.
The indicator problem
Water utilities test constantly for coliform bacteria, and a clean coliform result is often reported as though it settles the question. It does not, and it was never meant to.
Coliforms are an indicator organism. Their presence suggests a pathway exists by which fecal contamination could be reaching the water; their absence suggests it probably is not. That is a genuinely useful signal, and it is not the same thing as a survey of what is in the water. A clean coliform test says nothing about Legionella multiplying in the hot water tank of the building you are standing in, and it is a poor proxy for chlorine-resistant parasites that behave nothing like the bacteria being counted.
Passing the test you are required to run is not the same as being free of the hazards you are not testing for. That is not an accusation against water utilities, which generally do difficult work well. It is a statement about what a test result means.
Where the regulation stops
Roughly 43 million Americans — about 15 percent of the population — drink from private wells. Those wells are not regulated by the federal government under the Safe Drinking Water Act, and, as the EPA notes, not by most state governments either. There is no mandatory testing, no required treatment, and no one who sends a report.
The outbreak data shows the shape of that gap. Individual and private systems accounted for just 17 outbreaks in the 2015–2020 period — 8 percent of the total — but 944 cases, which is 44 percent of all illness, and 14 deaths. Among enteric outbreaks where the water source could be identified, wells accounted for 13 of 14.
The causes were mostly structural rather than exotic. Contamination through limestone and fissured rock. Improper well construction. Flooding and heavy rain. And, in a quarter of enteric outbreaks, a treatment deficiency — most often no disinfection at all, sometimes no filtration.
The size of the problem
Outbreak surveillance captures clusters that someone noticed, investigated and reported. It is a floor, not a total. To estimate the real burden, CDC researchers modeled 17 pathogens across every water exposure route for a single year, 2014, and published the result in Emerging Infectious Diseases.
Their estimate: 7.15 million waterborne illnesses annually in the United States, around 601,000 emergency department visits, roughly 117,900 hospitalizations, about 6,630 deaths, and $3.33 billion in direct healthcare costs.
Drinking water specifically accounted for an estimated 1.13 million illnesses — but 47,700 hospitalizations, 3,300 deaths and $1.39 billion, the largest share of the cost. The pattern holds: drinking water produces fewer illnesses than recreational water and far more of the serious outcomes.
And the cost is dominated by organisms that grow in plumbing rather than organisms that arrive in it. Nontuberculous mycobacteria accounted for 46 percent of direct costs, followed by acute otitis externa at 17 percent, Pseudomonas pneumonia at 14 percent and Legionnaires’ disease at 12 percent.
What you can actually find out
If you are on a community water system, your utility is required to publish an annual Consumer Confidence Report. It will tell you what was detected, at what level, and against which limit. It is a genuinely informative document and almost nobody reads it.
What a CCR will not tell you is what happened to the water between the main and your tap, because that stretch is not the utility’s to monitor. The temperature of your water heater, how long water sits in unused lines, and the age and material of your plumbing are all on your side of the meter.
If you are on a well, the position is simpler and harder: nobody is testing it, so the only results that exist are the ones you pay for. State and county health departments generally maintain lists of certified laboratories.
The thirty years since Milwaukee have produced better filtration standards, tighter turbidity limits and a surveillance system that catches more than it used to. They have also revealed that the hazard moved. It is no longer mainly a question of what gets into the reservoir. It is increasingly a question of what grows in the pipes afterwards — and that is a part of the system no treatment plant can reach.
This article is general information about waterborne pathogens and public health data. It is not medical advice, and it does not describe or evaluate any particular treatment equipment. If you have a specific health concern, speak to your doctor; if you have a specific water concern, start with your utility’s report or a certified laboratory.
In June the City of Tulsa published its 2026 Water Quality Report, covering everything the utility measured through 2025. The short version: the water met or exceeded every state and federal requirement, across more than 47,000 individual tests.
The first thing worth saying about Tulsa water is the least dramatic: the report is the report, and the people running the system are doing the job well.
What 47,000 tests actually buys you
Your water starts in four lakes — Oologah, Spavinaw, Eucha and Hudson — and passes through one of two treatment plants, Mohawk or A.B. Jewell, before it reaches your street. Both plants hold 5-Year Presidents Awards from the American Water Works Association’s Partnership for Safe Water, which is an award you only get by voluntarily holding yourself to a standard tighter than the law requires, and then proving it year after year.
Eric Lee, the city’s Director of Water and Sewer, put it this way when the report came out: “Every time someone turns on their faucet, there’s an entire team of people working behind the scenes to make sure the water is safe, reliable and there when they need it.” That is not a marketing line. It is roughly 130 tests a day, every day, for a year.
The PFAS result, and why it is worth knowing
The EPA required utilities to monitor for PFAS — the group of industrial compounds that has been in the news for a decade and in litigation for longer. Tulsa found no detectable levels. None. The same monitoring found no detectable lithium.
That result is worth holding on to, because PFAS is currently the most effective thing anyone can frighten a homeowner with. An approach that opens with PFAS in Tulsa is working from national headlines rather than local sampling data. The utility looked, and did not find it.
It is also worth knowing what home equipment does and does not cover. Whole-home carbon and ultrafiltration systems are generally certified under NSF/ANSI 42 and 53, which address aesthetic effects and specific contaminants such as cysts — not PFAS, lead, arsenic, pesticides or herbicides. Point-of-use reverse osmosis is certified under NSF/ANSI 58, and a listing under that standard covers the one tap it is fitted to rather than the house. Whatever the product, the certification is per claim and per model, and it is published.
So what is a filter for, then?
Here is the distinction that gets deliberately blurred in this industry. “Safe” is a legal threshold. It is not the same as “nothing in it,” and it was never meant to be. A utility’s job is to deliver water that will not make you ill, to every house on the network, at a price the city can sustain. It is not to deliver water that tastes like a mountain spring at your particular kitchen tap.
Tulsa publishes its treatment process, and it is worth reading, because it tells you exactly what is in your water on purpose. After filtration the city adds fluoride, then chlorine, then sodium hydroxide for corrosion control — and then ammonia, right as the water leaves the plant. Five things survive that process and arrive at your tap. Here they are.
One: chloramine, not chlorine
This one catches out most people selling filters in this city, so it is worth getting right. Tulsa does not send free chlorine down the mains. It adds ammonia on the way out of the plant, which converts the chlorine into chloramine — a more stable disinfectant that survives the journey better and, importantly, forms fewer regulated disinfection byproducts along the way. That is a deliberate, sensible choice, made by a lot of utilities for the same reason.
It also changes what a filter has to do. Chloramine is more stubborn than free chlorine: carbon takes it out, but it needs longer contact with more carbon to do it. So the question to put to any filter is precisely which claim its certification covers. A cartridge certified to NSF/ANSI 42 for chlorine taste and odor is certified for chlorine. Chloramine is a separate claim, and the two are easy to confuse on a box.
Two: cysts
Cryptosporidium and Giardia are microscopic parasites that arrive in surface water, and every drop of Tulsa’s water starts in a lake. They matter here for one specific reason: they are the thing disinfection handles least well. Crypto in particular shrugs off chlorine at the doses used in drinking water, which is why the EPA regulates it through filtration requirements rather than disinfection, and why the city’s sand and carbon filter beds are doing the real work rather than the chemistry.
The plant is meeting that standard — the report says so. A certified cyst-reduction stage inside a house is therefore not a fix for a failure; it is a second barrier, sitting after miles of main that the plant cannot see. Where equipment carries that claim it is NSF/ANSI 53 certification for cyst reduction specifically, which is not the same as a bacteria or virus claim. Those are different certifications, and cyst reduction does not imply them.
Three: fluoride, which is there on purpose
Tulsa adds fluoride after filtration, deliberately, to reduce tooth decay. The city has been clear that it intends to keep doing so. Major public health bodies support community fluoridation at the recommended level, and plenty of people are glad of it. Others would rather not drink it. That is a question for each household to settle, and this article is not the place it gets settled.
What is worth stating plainly is the engineering, because this is where a lot of money gets wasted. A whole-home carbon system does not remove fluoride. Carbon is the wrong tool for a dissolved ion that small, whoever is selling it. Fluoride reduction is a reverse osmosis claim under NSF/ANSI 58, and reverse osmosis is fitted at a single tap. Treating every shower and every toilet cistern to address fluoride would be an expensive way to solve a problem that lives at the kitchen sink.
Four: sediment from the last hundred feet
Between the plant and your shower there is distribution main, a service line, and your own household plumbing. Sediment gets picked up along the way, and the older the run, the more of it. This is also why the city’s True Reads program has been inspecting service line materials and upgrading meters — the last stretch matters, and it is not all the city’s to control.
Five: hardness, which nobody regulates
There is no federal limit on dissolved calcium and magnesium, because they do not hurt you. They hurt your water heater, your dishwasher, your kettle and your shower glass. Nothing in a water quality report will ever flag this as a problem, and it is the thing most Green Country homeowners actually notice first.
Where the money usually gets wasted
If the only complaint is the taste of drinking water, a whole-home system is the wrong shape of answer. Point-of-use reverse osmosis addresses that at a fraction of the cost. The same goes for fluoride: a one-tap problem has a one-tap answer, and paying to treat the whole house for it buys nothing extra.
If you are on Tulsa city water and someone quotes you a system sized for a private well, ask them why. Well water and municipal water are different problems with different equipment, and the difference is thousands of dollars.
And a hardness figure quoted for a specific address without a measurement is worth questioning. Hardness in Tulsa varies by source lake and by season, and the city publishes its own figures by treatment plant.
How to read your own report
None of this requires a middleman. The full 2026 report is published free at cityoftulsa.org/waterquality, and it is more readable than you would expect. Two things to look for: the detected range for each contaminant next to its legal limit, which tells you how much headroom there is, and the footnotes, which is where a utility explains anything unusual.
One caveat on any utility report, this one included: it describes water as it leaves the plant and as sampled across the distribution system. It does not describe the plumbing inside any particular building, which is why a figure in the report and a figure at a kitchen tap can differ without either being wrong.
Have we been to your sink?
Tell people what actually happened — what we tested, what we told you, whether it helped. Thirty seconds, and it is the main way our neighbors find us.
On-site work is offered in these counties only, at this time. We would rather cover a small area properly than a large one badly. If you are just outside and think it is worth the drive, ask us anyway — we will give you a straight answer.
Outside these counties?
You can still buy any system from us and have it shipped anywhere in Oklahoma. For plumbers and water treatment technicians working outside the metro, we offer a virtual consultation — a call, screen to screen, covering sizing, fitting and anything the spec sheet does not answer. There is no charge for it, and you do not have to be buying from us that day.
We ship and install within Oklahoma only. Shipping and Oklahoma sales tax are calculated at checkout. Payment is handled by Stripe — your card details never touch our site.